An Anion Gap Calculator is a practical diagnostic tool for interpreting blood chemistry results and detecting patterns that may indicate an acid-base problem. In outpatient assessment, it supports providers and patients understand an electrolyte panel or basic metabolic panel by evaluating measured sodium, chloride, and bicarbonate values. The result is the anion gap, a useful screening marker for certain forms of metabolic acidosis and broader electrolyte imbalance.
Because ambulatory lab testing is often reviewed outside an acute care setting, the context matters. Small changes in serum electrolytes can suggest hydration status, renal function, medication effects, or a metabolic disturbance that requires follow-up testing. The anion gap is not a final causal diagnosis, but it is a useful clue in clinical interpretation.
What the Anion Gap Measures
The anion gap estimates the gap between the main positively charged and negative particles in serum electrolytes. In plain language, it indicates the presence of unmeasured anions in the blood. Those unmeasured ions can rise in some disease states, especially when acid-base status is disrupted.
Most routine blood chemistry panels measure sodium, chloride, and bicarbonate directly. These values are used because they are readily available on an electrolyte panel or basic metabolic panel. The calculation helps reveal whether a patient may have metabolic acidosis, particularly high anion gap metabolic acidosis, where acids collect faster than the body can clear them.
In outpatient labs, the anion gap serves as a screening marker rather than a stand-alone answer. A above-normal value may point toward lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. A decreased or normal value can also be meaningful, especially when hypoalbuminemia, paraproteinemia, or lab error is present.
How to Use an Anion Gap Calculator
Using Anion Gap Calculator is simple. You enter the available serum electrolytes from the lab report, usually sodium, chloride, and bicarbonate. The calculator performs the arithmetic and returns the anion gap value, which can then be compared with the expected reference range.
For most outpatient lab review, the key is to use the values exactly as reported and verify whether the laboratory uses a standard or albumin-adjusted method. The calculator is especially helpful when reviewing a basic metabolic panel because it can quickly highlight a possible acid-base disorder that otherwise might be missed during routine lab interpretation.
Here is the typical workflow:
- Add the sodium value from the blood chemistry report. Enter the chloride value. Input the bicarbonate value, sometimes reported as CO2 or total CO2. Review the calculated anion gap against the expected reference range. Determine whether albumin should be used for correction.
In outpatient assessment, the calculator is most useful when paired with the rest of the laboratory results and the patient’s symptoms. A single number should not override the broader clinical context, especially if there is an electrolyte imbalance, dehydration, medication exposure, or renal function abnormality.
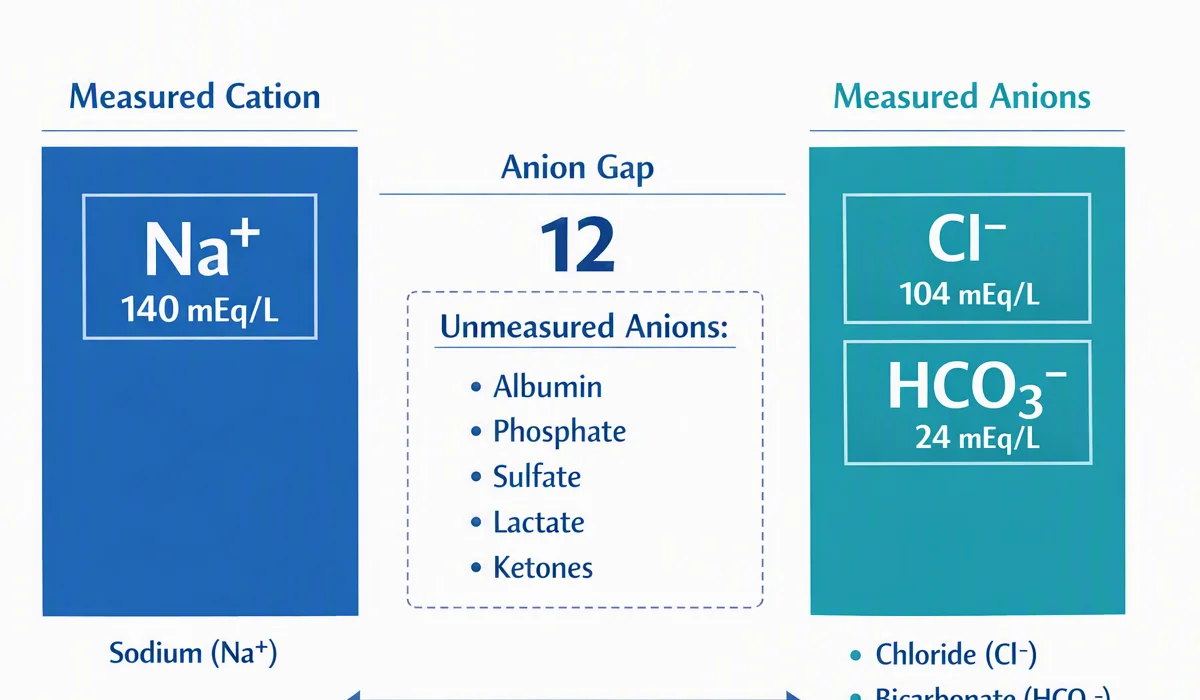
Anion Gap Formula and Variations
The classic anion gap formula is:
Anion gap = sodium − (chloride + bicarbonate)
This calculation formula applies the measured serum electrolytes to approximate the amount of unmeasured anions. In most labs, the expected reference range is narrow, but the exact range can vary depending on the analyzer and reporting method. That is why outpatient lab interpretation should always take into account the lab’s own stated range.
A major variation is the albumin correction. Since albumin is a negatively charged protein, low albumin can make the anion gap look falsely low or normal. When albumin is reduced, the albumin-corrected anion gap can show a hidden high gap that would otherwise be missed. This adjusted, or corrected value, is especially important in patient evaluation when there is undernutrition, chronic disease, inflammation, or liver-related illness.
Albumin correction is commonly used because albumin contributes substantially to the pool of unmeasured anions. In practical lab interpretation, this means a patient with hypoalbuminemia may have a “normal” anion gap that is not genuinely normal after adjustment. The corrected number supports clinical interpretation and supports more accurate identification of an acid-base disorder.
Different institutions may use slightly different methods for the reference range and the albumin correction equation. That is another reason the anion gap should be treated as part of a larger diagnostic tool set, not as a standalone answer.
Understanding a High Anion Gap in Outpatient Labs
A high anion gap typically indicates that unmeasured acids are present in excess, which can suggest high anion gap metabolic acidosis. In outpatient labs, this finding should lead to careful review of the patient’s symptoms, medication list, renal function, and possible exposures. The leading causes include lactic acidosis, ketoacidosis, and uremia.
Lactic acidosis can occur when the body produces more lactate than it can clear. In outpatient assessment, this may be related to poor perfusion, severe illness, medication effects, or other metabolic disturbance. Ketoacidosis may be seen with diabetes, fasting, heavy alcohol use, or prolonged poor intake. Uremia reflects advanced impairment in renal function and can elevate the anion gap as acids accumulate.
Other causes of high anion gap metabolic acidosis include toxic alcohols, salicylates, and less common metabolic conditions. While this article centers on outpatient lab interpretation, a markedly elevated value should never be ignored. It may suggest a clinically significant acid-base balance problem that needs prompt supportive testing and follow-up.
A practical point in outpatient labs is that symptoms may be subtle or absent. Mild nausea, fatigue, shortness of breath, or confusion may be the only clues. Because of that, the anion gap works best as a screening marker that initiates further clinical interpretation, not as a final diagnostic endpoint.
Interpreting a Normal or Decreased Anion Gap
A normal anion gap does not rule out disease. In fact, normal anion gap metabolic acidosis can still be detected even when the anion gap looks ordinary. In those cases, the issue is usually a decrease of bicarbonate that is balanced by a rise in chloride, rather than buildup of unmeasured acids.
A decreased anion gap is less common, but it merits attention in outpatient labs. The main causes include hypoalbuminemia, paraproteinemia, and lab error. Low albumin lowers the baseline amount of unmeasured anions and can make the result appear artificially low. This is why the albumin-corrected anion gap is very helpful for more reliable clinical interpretation.
Paraproteinemia, such as from monoclonal proteins, can change the charge balance in blood chemistry and influence the anion gap. In these cases, a low or unexpectedly normal result may be a clue to a separate underlying problem rather than a harmless finding. Meanwhile, lab error remains an significant possibility whenever the result does not fit the clinical picture. Rechecking the specimen or repeating the electrolyte panel may be the first step.
In outpatient assessment, a low or normal result should be evaluated alongside symptoms, albumin, kidney function, and the overall lab trend. The goal is to avoid overcalling a benign finding while also not missing a hidden disorder.
Common Causes of Unusual Findings
Unexpected anion gap findings often indicate a limited set of key issues. In ambulatory care, the most common causes consist of toxic ingestion, renal failure, and dehydration. All of these can affect serum electrolytes and acid-base balance in different ways.
Toxic ingestion may include substances like toxic alcohols, which can produce a dangerous high gap by producing unmeasured acids. This is a common cause of high anion gap metabolic acidosis and should be suspected when the laboratory pattern is striking or the history suggests exposure.
Renal failure limits acid excretion and can elevate the anion gap as metabolic waste accumulates. Even small changes in renal function may influence the lab pattern, especially when paired with medication use or dehydration. In outpatient labs, kidney-related anion gap clinical significance changes often warrant repeat testing and trend review rather than a single decision.
Dehydration can increase blood chemistry values and sometimes uncover a metabolic disturbance that was harder to see before. While dehydration alone does not fully explain every abnormal anion gap, it can aggravate electrolyte imbalance and increase other abnormalities. A detailed patient evaluation should consider oral intake, fluid losses, and recent illness.
Other additional factors can include poor nutrition, chronic illness, diabetes, and medication effects. The main point is that the anion gap should always be treated as part of a more comprehensive workup, not a stand-alone conclusion.
Clinical Points for Ambulatory Settings
Additional readingClinic labs require a different mindset than acute testing. Results are often evaluated after the fact, which means the patient may be unchanged, recovering, or fully without symptoms. That makes clinical context crucial for accurate lab interpretation. The same result can have quite different meaning depending on the setting.
As an example, a mild anion gap elevation in a patient with known diabetes, vomiting, or poor intake may point to ketoacidosis. A comparable value in someone with chronic kidney disease could reflect renal function changes or a progressive metabolic disturbance. In a patient with low albumin, the uncorrected result may miss the true acid-base disorder. This is where the albumin-corrected anion gap becomes particularly useful.
Ambulatory labs also benefit from follow-up testing. Rechecking the electrolyte panel, checking albumin, reviewing the basic metabolic panel trend, and ordering supportive testing can help clarify whether the result is temporary or ongoing. If the initial result suggests high anion gap metabolic acidosis or another acid-base imbalance, additional blood chemistry studies may be needed to find the cause.
Another outpatient factor is that a slight abnormality may not require urgent action if the patient is well and the trend is stable. Still, unexplained changes need attention, especially when accompanied by symptoms or risk factors for toxic alcohols, ketoacidosis, renal failure, or lactic acidosis. Good outpatient assessment strikes caution with context.
Ultimately, the Anion Gap Calculator is most effective when used as part of a systematic approach to patient evaluation. It helps clinicians identify abnormal patterns, decide when further workup is warranted, and interpret laboratory results in light of the overall clinical picture.
Common Questions
What is an anion gap calculator used for?
An anion gap calculator is used to evaluate blood chemistry results by measuring the difference between measured cations and anions. It helps spot possible metabolic acidosis, especially high anion gap metabolic acidosis, and improves clinical interpretation of outpatient labs.
How do you calculate anion gap from sodium, chloride, and bicarbonate?
The standard calculation formula is sodium minus the sum of chloride and bicarbonate. Put another way, anion gap = sodium − (chloride + bicarbonate). This uses values from an electrolyte panel or basic metabolic panel to approximate unmeasured anions.
What’s the normal anion gap range?
Reference ranges differ depending on the lab and analyzer, so the normal anion gap range should always be compared with the lab’s stated reference range. Some laboratories may list different values depending on whether albumin correction is used.
Why do you correct the anion gap for albumin?
Albumin correction is used because low albumin can hide an elevated gap. Albumin is a major unmeasured anion, so hypoalbuminemia can make the result appear low even when an acid-base disorder is present. Albumin correction improves the corrected value and makes interpretation more reliable.
What does a high anion gap mean in outpatient lab results?
A high anion gap in outpatient lab results usually suggests excess unmeasured acids and may indicate lactic acidosis, a ketotic state, renal failure, or toxic alcohols. It should be interpreted with patient context, symptoms, and follow-up testing rather than as a sole diagnosis.