What the anion gap Evaluates
The anion gap is a practical way to evaluate the connection between measured electrolytes in a serum chemistry panel and the body’s overall acid-base balance. It reflects the difference between common positively charged and negatively charged ions and assists identify whether an acid-base disorder is present, especially metabolic acidosis. Clinicians rely on it as a diagnostic aid because an abnormal result can indicate extra acids in the blood or to a shift in the balance of ions that would otherwise be missed on routine lab values.
At its core, the anion gap reflects unmeasured anions in the blood. These are substances not directly listed on a basic electrolyte panel, yet they influence the overall charge balance. When these unmeasured acids rise, the gap often rises, creating a high anion gap. When the balance is altered by low protein levels, excess positively charged proteins, or testing issues, a low anion gap may be seen. A normal anion gap does not always mean everything is fine, but it can clarify the differential diagnosis and guide next steps in clinical interpretation.
Because serum chloride is part of the calculation, a change in chloride concentration can greatly influence the result. That is why a practical anion gap calculator is more useful than memorizing the concept alone. It links the raw blood chemistry values to the likely physiologic pattern behind the abnormality.
How to Work with an Anion Gap Calculator with Serum Chloride
An anion gap calculator generally takes serum sodium, serum chloride, and serum bicarbonate. Certain calculators also include serum potassium. The goal is to compare the primary measured cations with the primary measured anions and determine the remaining gap. This is especially helpful when reviewing an electrolyte panel in a patient with suspected metabolic acidosis or other electrolyte imbalance.
To use the calculator correctly, enter the values exactly as reported by the laboratory. Even small differences in serum chloride or serum bicarbonate can alter the result enough to move the interpretation from a normal anion gap to an elevated anion gap or vice versa. If potassium is included, the calculator may give a slightly increased result, but many clinicians use the version without potassium for uniformity.
Here is a simple sequence:
- Check the most recent serum sodium, serum chloride, and serum bicarbonate. Check whether the calculator uses serum potassium or leaves out it. Submit the lab values exactly as reported. Assess the output in the context of the patient’s symptoms and other lab values. If the result is surprising, think about repeat testing and broader clinical interpretation.
The calculator is best viewed as a diagnostic aid, not a self-contained answer. Its value increases when paired with the patient’s history, medication use, kidney function, and blood gas results. In that context, the anion gap becomes a practical way to assess acid-base balance rather than just a number on a screen.
Anion Gap Formula and Calculation Inputs
The standard calculation formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some equations include serum potassium:
Anion gap = (serum sodium + serum potassium) - (serum chloride + serum bicarbonate)
This version omitting potassium is used often because potassium is usually small relative to the other ions and may vary less in everyday interpretation. Still, knowing whether potassium is included matters when comparing results across different calculators or reports. The key inputs are the chloride level and bicarbonate level, since these values directly affect the final number.
Each input represents part of the body’s serum chemistry profile. Sodium is the main measured cation, while chloride and bicarbonate are the main measured anions in routine testing. If bicarbonate drops, the gap may rise if chloride does not rise enough to offset the change. If chloride rises, the gap may fall even if the patient still has an acid-base problem. That is why the formula must be interpreted together with the full electrolyte panel and the clinical setting.
For practical use, remember that the anion gap is not measuring a single toxin or acid. It is estimating the presence of unmeasured anions and helping identify whether there is an anion deficit or a hidden acid load. This is especially valuable in metabolic acidosis, where the pattern of sodium, chloride, and bicarbonate can point toward different underlying causes.
Normal Anion Gap Range and Assessment
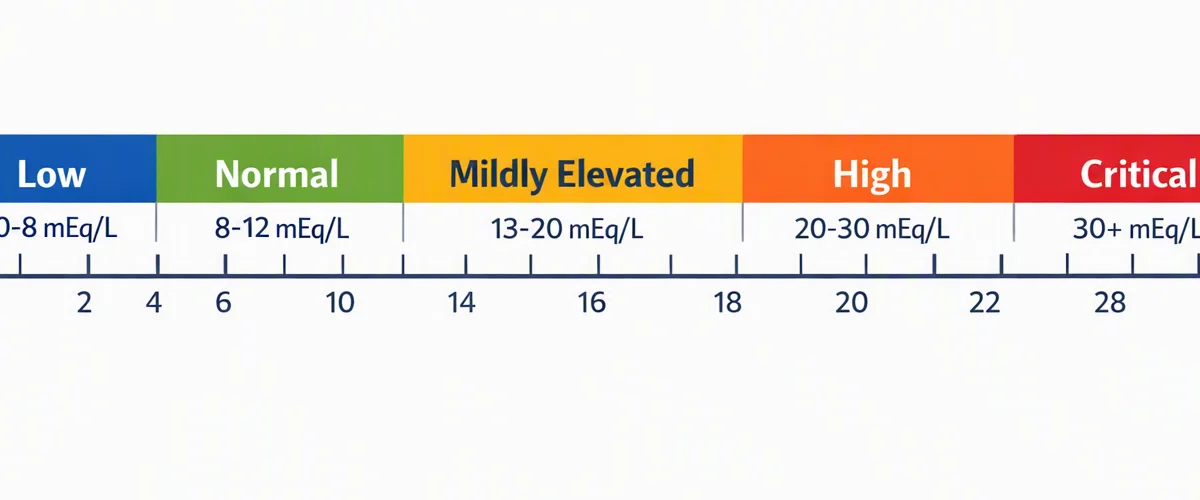
The normal range for the anion gap can differ by laboratory because of differences in methods and reporting standards. This is why the reference range from the local lab should typically be used when available. In general, a result within the expected limits suggests no obvious excess of unmeasured acids, but it does not rule out all disorders.
A high anion gap often indicates additional acids in the blood, while a normal anion gap may suggest that bicarbonate loss is being balanced by a rise in chloride. This pattern is common in some forms of non-gap metabolic acidosis. A low anion gap is uncommon and often reflects low albumin, lab issues, or unusual protein states.
Interpretation should always review the overall pattern:
- High anion gap: points to extra unmeasured acids. Normal anion gap: may reflect a chloride-driven bicarbonate loss or no major gap abnormality. Low anion gap: may indicate hypoalbuminemia, testing error, or excess positively charged proteins.
The important point is that a single result does not define the patient’s condition. The anion gap is one piece of a larger acid-base assessment that includes symptoms, kidney function, medication review, and other labs. Its main strength is in pattern recognition, especially when paired with clinical interpretation.
Causes of an Elevated Anion Gap
A high anion gap usually indicates there appear higher levels of unmeasured acids in the bloodstream than usual. Common causes include lactic acidosis, ketoacidosis, renal failure, and ingestion of toxic alcohols. Every one of these conditions can create a distinctive acid base pattern that becomes more apparent when the anion gap is calculated.
Lactic acidosis occurs when lactate builds up, often because tissues are not receiving enough oxygen or because metabolism is disrupted. Ketoacidosis is associated with ketone production, often seen in diabetes, starvation, or prolonged vomiting. Renal failure can reduce the body’s ability to clear acids, allowing them to accumulate. Toxic alcohols such as methanol or ethylene glycol can also raise the gap because their metabolites are acidic and dangerous.
In many of these settings, the anion gap provides a practical clue before the cause is fully known. That makes it a useful part of toxicity screening and acid-base review. Still, the number itself does not distinguish one diagnosis from another. A patient with severe metabolic acidosis and a high gap may need urgent evaluation to determine whether the cause is lactic, ketotic, renal, or toxic.
Further clues help refine the assessment:
- Elevated lactate supports lactic acidosis. Hyperglycemia and ketones suggest ketoacidosis. Rising creatinine may point toward renal impairment or renal failure. Exposure history raises concern for toxic alcohols.
Reasons for a Decreased or Subzero Anion Gap
A reduced anion gap or even a subzero reading is uncommon and should require careful review. One common cause is hypoalbuminemia, since albumin is a key negatively charged protein that contributes to the gap. When albumin is low, the gap may seem artificially reduced even if the acid-base state is otherwise unchanged.
Another possibility is testing error or other measurement issue. A mislabeled sample, instrument issue, or specimen problem can distort sodium, chloride, or bicarbonate values. Because the formula depends on these inputs, even a minor error can shift the result significantly. This is why unexpected values often merit repeat testing.
Less frequent but significant causes include multiple myeloma and other forms of paraproteinemia. In these conditions, abnormal proteins can alter the charge balance and lower the measured gap. A low anion gap should not be ignored if the patient has anemia, kidney dysfunction, bone pain, or other https://anion-gap-formula837.trexgame.net/how-to-work-with-an-anion-gap-calculator-when-albumin-is-low signs that might suggest a plasma cell disorder.
Common reasons to review a low or negative result include:
- Hypoalbuminemia Lab error Multiple myeloma Paraproteinemia
Because low values can be confusing, the anion gap should always be reviewed in the full clinical context. A low result may be a clue, but it is rarely the complete explanation by itself.
In what way Serum Chloride Influences the Computation
Serum chloride has a significant role in the anion gap because it sits directly in the formula. A elevated chloride value lowers the calculated gap, while a lower chloride value can elevate it. This means changes in chloride can alter the apparent balance even if the underlying disease process has not changed. Understanding this relationship is important for accurate interpretation.
Hyperchloremia can drive the gap downward and is often seen when bicarbonate falls but chloride rises to maintain electrical neutrality. This pattern is typical in some forms of non-gap acidosis. Hypochloremia, on the other hand, may lead to a elevated calculated gap by reducing the subtraction term in the formula. Both patterns are instances of electrolyte imbalance affecting the final result.
This is why the anion gap is more informative when reviewed with the full electrolyte pattern. A patient may have a apparently normal gap simply because chloride has risen enough to offset bicarbonate loss. Another patient may show a increased gap because chloride is not elevated despite a major acid load. The relationship between sodium, chloride, and bicarbonate is part of the body’s compensatory mechanism and should be evaluated carefully.
Corrected Anion Gap and Albumin Adjustment
Albumin plays a major role affecting the anion gap because it bears a negative charge. When albumin is low, the measured gap may appear reduced than it truly is. That is why albumin correction is often recommended when evaluating the result in patients with low protein levels or suspected chronic illness.
A corrected anion gap modifies the reported value upward to account for reduced albumin. While formulas can vary by institution, the overall purpose is the same: to avoid underestimating hidden acids when hypoalbuminemia is present. This is anion gap clinical significance especially important in critically ill patients, where albumin may reflect nutrition, inflammation, or illness severity.
Assessing protein status helps determine whether the reported gap is truly normal or simply masked by low albumin. In practice, the corrected value can reveal a hidden high anion gap that would otherwise be missed. That said, albumin correction is an aid, not a replacement for clinical judgment.
When albumin is low, review:
- Whether the uncorrected gap may underestimate acid burden Whether the patient has chronic illness or malnutrition Whether the corrected result changes the interpretation
Interpreting Results with Other Lab Values
The anion gap becomes much more useful when interpreted with an arterial blood gas. A blood gas helps confirm whether the patient actually has acidemia or alkalemia and shows whether bicarbonate changes are part of a broader acid-base disorder. The measured pH provides the clearest immediate view of acidemia, while bicarbonate and carbon dioxide help distinguish metabolic from respiratory causes.
Blood gas analysis is especially helpful when the anion gap is abnormal but the patient’s symptoms are not obvious. For example, a high gap with low pH and elevated lactate strongly supports lactic acidosis. A high gap with ketones suggests ketoacidosis. If pH is near normal, there may be mixed processes or a strong compensatory mechanism masking the severity of the disorder.
Other lab values can aid narrow the source:
- Lactate for likely lactic acidosis Ketones for likely ketoacidosis Creatinine and blood urea nitrogen for renal failure Osmolal gap or exposure history for toxic alcohols
Using the anion gap with an arterial blood gas offers more accurate clinical interpretation. In combination, these tests can reveal whether the patient has a underlying metabolic problem, a respiratory compensation pattern, or a mixed disturbance.
Limitations, Common mistakes, and When to Seek Clinical Review
Although the anion gap is useful, it has notable limitations. The result can be influenced by measurement error, changing lab methods, and changes in protein concentration. It should never be interpreted in isolation. The same number may mean different things depending on the patient’s history, medications, kidney function, and overall clinical context.
One common pitfall is assuming that a normal value rules out acid-base disease. A patient can still have a serious disorder with a normal gap, especially if chloride has risen to offset bicarbonate loss. Another pitfall is overlooking a low gap caused by hypoalbuminemia or paraproteinemia. It is also important not to overcall an abnormal result when there may be a simple analytical issue that deserves repeat testing.
Seek medical evaluation when the result is unexpected, when there are symptoms such as confusion, rapid breathing, or severe weakness, or when there is suspicion of serious causes such as lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. Results should also be reviewed promptly if there is concern for multiple myeloma, unexplained paraproteinemia, or persistent electrolyte abnormalities.
In short, the anion gap is most valuable when it is used as part of a broader interpretation strategy rather than as a standalone label. A careful review of serum chloride, sodium, bicarbonate, potassium, albumin, and blood gas data helps turn a calculator result into useful clinical insight.
FAQ
How do you work out anion gap using serum chloride?
Use the common formula: serum sodium minus the sum of serum chloride and serum bicarbonate. Certain formulas also include serum potassium. The key idea is that serum chloride is subtracted along with bicarbonate, so changes in chloride can greatly change the result.
What is a high anion gap a sign of?
A high anion gap usually suggests extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. It often points to metabolic acidosis, but the exact cause still needs clinical review.
Does a low albumin level alter the anion gap?
Yes. Albumin is a major negatively charged protein, so hypoalbuminemia can lower the measured anion gap. In that situation, albumin correction may be needed to avoid missing a hidden high anion gap.
Why does serum chloride matter in the anion gap formula?
Serum chloride is one of the main terms in the formula, so it directly affects the calculation. Higher chloride lowers the gap, while lower chloride raises it. This is why hyperchloremia and hypochloremia can change how the result is interpreted.
When should an anion gap result be reviewed by a clinician?
It should be reviewed when the result is abnormal, unexpected, or inconsistent with the patient’s condition. Clinical review is especially important if there are signs of metabolic acidosis, elevated lactate, suspected toxic alcohol exposure, renal failure, or concern for measurement error, multiple myeloma, or paraproteinemia.