How this Anion Gap Measures
The anion gap is a helpful way to assess the balance of charged particles in the blood, especially when evaluating acid-base balance. It is computed from standard serum electrolytes and helps clinicians calculate anion gap results as part of a more complete metabolic acidosis evaluation. In most cases, the calculation uses sodium, chloride, and bicarbonate from an electrolyte panel.
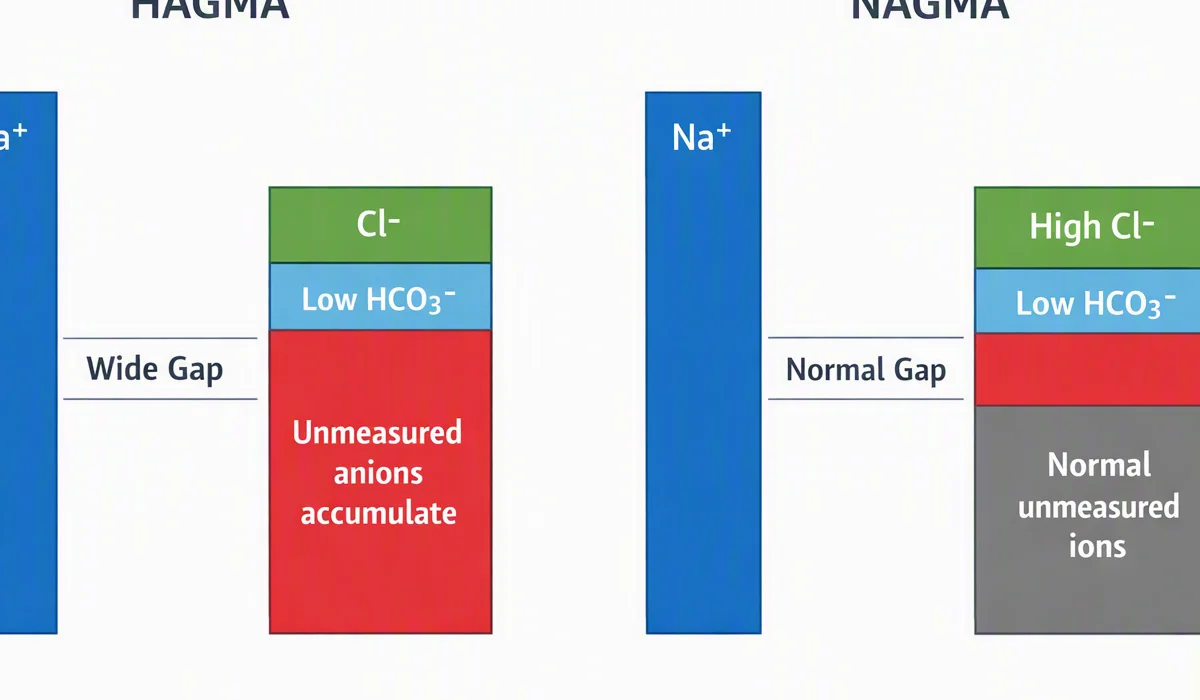
This number is not a direct measurement of acids. Instead, it approximates the amount of unmeasured anions in the blood. Those unmeasured substances can rise in metabolic acidosis, making the anion gap a useful diagnostic tool for detecting unexpected acidosis. It is especially helpful when reviewing serum bicarbonate level changes that may suggest an acid-base problem even before the full picture is obvious.
The anion gap is often used to help interpret lab results when the delta gap value calculator cause of acidosis is not obvious at once. A high value can point to extra acids in the blood, while a normal value can indicate other forms of acid loss or replacement. Because the calculation is based on everyday serum electrolytes, it is widely available and easy to follow over time.
Why Albumin Changes the Anion Gap
Albumin is one of the major protein bound anions in plasma, so it has a significant effect on the calculated anion gap. When albumin is low, the gap may look smaller than it really is because fewer negatively charged proteins are present to contribute to the total. This is why hypoalbuminemia can obscure a real acid-base problem.
To account for this, clinicians use albumin correction to calculate a corrected anion gap. This adjusted value is often called the albumin adjusted anion gap. It helps correct for albumin so that the result better represents the actual presence of unmeasured anions.
This correction matters because a normal-looking anion gap may not be truly normal when albumin is reduced. In patients with low serum albumin level, the uncorrected number can underestimate the severity of metabolic acidosis. That means albumin adjustment improves the value of the result for clinical interpretation and may improve diagnostic accuracy.
In short, albumin changes the anion gap because it is a major contributor to the negative charge in plasma. If albumin falls, the measured gap often falls too, even when the underlying acid-base disorder has not improved.
How to Work With an Anion Gap Calculator
An Anion Gap Calculator makes easier the step of finding and adjusting the gap. To work with it, you typically enter the values for sodium, chloride, bicarbonate, and albumin. The calculator then uses the anion gap formula and, when needed, the albumin adjustment on its own.
The basic workflow is easy to follow:
- Add the sodium value from the lab report. Enter chloride and bicarbonate values. Input the albumin value if albumin correction is needed. Review the calculated anion gap and the corrected anion gap. Contrast the result with the reference range used by the lab.
This process allows clinicians and learners interpret lab results efficiently, especially when evaluating acid base status. It also cuts down on arithmetic mistakes and aids faster recognition of electrolyte imbalance patterns. For practical use, the calculator serves as a fast diagnostic tool that can help screen for hidden acidosis.
When reviewing the result, remember that the calculator is only a single part of the overall picture. The numbers must still be interpreted in context with the patient’s symptoms, history, and other laboratory findings.
Anion Gap Assessment with Albumin Adjustment Formula and Computation Steps
The standard anion gap formula is:
Anion gap = sodium − (chloride + bicarbonate)
The result is typically reported in mmol/L. The exact reference range can change by laboratory method, but the calculation itself is straightforward and broadly applied.
To apply albumin correction formula, a frequently used approach is to add a correction factor based on the patient’s albumin level. One traditional method adds approximately 2.5 mmol/L to the anion gap for every 1 g/dL decrease in albumin below normal. The specific method may vary by institution, so the laboratory reference range and local practice should always be checked.
A simple stepwise approach is as follows:
- Compute the initial anion gap using sodium, chloride, and bicarbonate. Review the serum albumin level. If albumin is low, apply the albumin correction. Review the albumin adjusted anion gap in mmol/L. Contrast both the raw and corrected values with the expected reference range.
Calculation example: If sodium is 140 mmol/L, chloride is 104 mmol/L, and bicarbonate is 20 mmol/L, the uncorrected anion gap is 16 mmol/L. If albumin is low, the corrected anion gap may be higher after adjustment, which could change the interpretation from borderline to clearly abnormal. That is why the calculator is helpful for both teaching and bedside clinical interpretation.
The purpose is not only to produce a number. It is to improve the acid-base analysis more accurate by accounting for changes in protein bound anions that alter the baseline.
Explaining High, Normal, and Low Anion Gap Results
A raised result often indicates high anion gap metabolic acidosis, which means extra acids or unmeasured anions are piling up. This pattern usually calls for a careful search for the underlying cause, especially if the bicarbonate is low and symptoms fit the picture.
A within-range result does not always eliminate a problem. Normal anion gap metabolic acidosis can occur when bicarbonate is lost and replaced by chloride, leaving the calculated gap unchanged. In these cases, the acid-base disturbance is present, but the gap is not elevated. That is why the full lab pattern matters so much in clinical interpretation.
A low anion gap is less common but still worth noting. It can occur with low albumin, lab variation, or unusual positively charged substances. A low value should not be ignored, especially if the patient has other signs of electrolyte imbalance or a broader acid-base problem.
In practice, the interpretation depends on the relationship between the gap, bicarbonate, chloride, and albumin. This is where the Anion Gap Calculator becomes especially useful because it helps separate a truly normal value from one that only appears normal because of hypoalbuminemia.
Important interpretation points include:
- Elevated gap: consider extra acids and metabolic acidosis. Normal gap: consider bicarbonate loss or chloride replacement. Low gap: check albumin, method issues, and unusual lab patterns.
Frequent Causes of Abnormal Anion Gap
A number of conditions are closely linked to abnormal anion gap values. Certain conditions elevate the gap because they increase acidity in the blood, while others decrease it indirectly by changing the protein or electrolyte balance.
Lactic acidosis is a well-known cause of high anion gap metabolic acidosis. When tissues are not adequately perfused or oxygen delivery is reduced, lactate accumulates and the gap rises. This is often seen in severe illness and is a major reason clinicians use the anion gap as part of metabolic acidosis evaluation.
Ketoacidosis is another common cause. In diabetic, alcoholic, or starvation states, ketone bodies add to the pool of unmeasured anions, elevating the gap. A high value in this setting often supports the diagnosis when the rest of the data align.
Renal failure can also increase the gap because the kidneys fail to clear acid efficiently. As acids accumulate, the bicarbonate falls and the gap may increase. This makes the anion gap a helpful clue in chronic or acute kidney dysfunction.
Toxic alcohols are another important cause to consider. Certain ingestions produce organic acids that elevate the gap and can cause dangerous acid-base derangements. In such cases, the anion gap may provide an early warning signal that requires urgent attention.
Additional causes can include severe tissue hypoperfusion, sepsis, or mixed toxic exposures. Because multiple processes can overlap, the calculator should be used as part of a broader clinical interpretation rather than as a standalone answer.
When to Correct the Anion Gap for Albumin
Adjusting for albumin is most useful when hypoalbuminemia is present. In patients with reduced albumin, the uncorrected anion gap may downplay the degree of acid accumulation, leading to missed or delayed recognition of metabolic acidosis.
Correction is particularly helpful in critical illness, where albumin often decreases and acid-base disorders are frequent. In this setting, relying on the raw number alone can weaken diagnostic accuracy. The adjusted value gives a clearer view of the true acid-base status and can help identify a hidden gap that would otherwise be overlooked.
It is also useful when the clinical picture suggests acidosis but the measured gap looks normal. In such cases, albumin adjustment can help clarify the discrepancy and improve acid-base disorders assessment. This is one reason the calculator is often used to screen for hidden acidosis.
Situations where albumin correction is often helpful include:
- Decreased serum albumin level Critical illness Uncertain acid-base balance abnormalities Likely unexpected acidosis with a borderline gap
In short, if albumin is low, the corrected value is usually more useful clinically than the uncorrected one.
Limitations and Clinical Caveats
Although the anion gap is helpful, it has important limitations. Multiple labs may use alternative measurement methods, which means lab variability can influence the result. A value that is within range in one setting may not be normal in another, so the local reference interval matters.
Another major caveat is the possibility of a mixed acid-base disorder. A patient may have more than one process at the same time, such as a high-gap acidosis plus a metabolic alkalosis. In that situation, the bicarbonate and anion gap may not behave in a simple way, and careful analysis is essential.
Likewise, a broader electrolyte imbalance can distort the interpretation. Changes in sodium, chloride, or bicarbonate can shift the number even when the underlying clinical condition anion gap clinical significance is complex. That is why the gap should always be interpreted alongside the full chemistry panel and clinical context.
Other caveats include unusual proteins, analytical differences, and the fact that albumin correction is an estimate rather than a perfect measurement. The adjusted result is useful, but it is still only one part of a full acid-base evaluation.
Best practice is to use the calculator as a reference, then confirm the pattern against symptoms, history, and related laboratory findings. That approach improves confidence in the final clinical interpretation.
Frequently Asked Questions
What is an anion gap calculator used for?
An Anion Gap Calculator is used to calculate and interpret the anion gap from common serum electrolytes. It helps clinicians evaluate acid-base balance, identify metabolic acidosis, and detect a possible hidden acid load when the routine lab pattern is not obvious.
How do you correct the anion gap for albumin?
To correct for albumin, first calculate the raw gap using sodium, chloride, and bicarbonate. Then apply an albumin correction factor based on the patient’s serum albumin level. Because low albumin lowers the measured gap, the adjustment produces a more accurate corrected anion gap.
What’s a normal anion gap value range?
The anion gap reference range depends on the laboratory’s technique and reference range. For that reason it is essential to read the result using the local local reference interval rather than using one universal number. The calculator allows you to compare the result with the relevant interval.
How does low albumin reduce the anion gap?
Albumin is a key source of negative charge in the blood because it contains bound anions. When albumin is low, there are reduced negative charges contributing to the gap, so the measured value falls. This is why hypoalbuminemia can make the gap seem falsely normal or low.
What conditions cause a high anion gap?
Common causes of a high gap include lactate acidosis, ketotic acidosis, renal insufficiency, and poisonous alcohols. These conditions add to unmeasured anions and often produce anion gap metabolic acidosis. The exact cause should be determined by the full clinical picture and supporting labs.