What Is the Anion Gap?
The anion gap is a calculated value that helps you evaluate acid-base status from standard lab tests. It is based on the connection between the main measured electrolytes in blood, especially sodium, chloride, and bicarbonate. Clinicians use it as a rapid diagnostic clue when reviewing lab results and trying to figure out whether there may be an acid-base disorder.
In practical terms, the anion gap helps compare positively charged ions with negatively charged ions in the bloodstream. Because a standard panel does not measure every ion directly, the anion gap calculator approach estimates the difference between measured values and can indicate an underlying problem such as metabolic acidosis. That is why it is often reviewed during lab interpretation of blood chemistry.
The value is commonly calculated from a comprehensive metabolic panel, also called a CMP, or from a related chemistry panel. Although it is not a diagnosis by itself, it helps assess whether the body may be dealing with an electrolyte imbalance or an abnormal accumulation of acids. The result becomes more useful when interpreted along with serum bicarbonate, serum albumin, and the full clinical picture.
Which CMP Values Do You Need?
To calculate anion gap from a CMP, you need only some specific values from the comprehensive metabolic panel. The core values are the sodium value, the chloride measurement, and the CO2 value reported on the panel. In many lab reports, CO2 is used as a proxy for bicarbonate.
The reason these values matter is that the calculation compares important measured electrolyte values in the blood. Sodium is the main measured cation, while chloride and bicarbonate are the main measured anions in the basic calculation. If you have a CMP in front of you, the relevant numbers are usually quick to identify in the serum electrolytes section.
Here is what to look for:
- Sodium — usually listed as Na Chloride — usually listed as Cl CO2 — often reflects bicarbonate in chemistry testing Potassium — optional, depending on the formula used
Some lab reports may also include serum albumin, which is useful if you want a more accurate corrected value. Albumin is not required for the basic calculation, but it becomes useful when evaluating whether the apparent result might be influenced by protein levels.
Anion Gap Calculator Formula
The conventional anion gap formula is easy to follow:
Anion gap = Sodium − Chloride − Bicarbonate
Using the anion gap calculator method, you can enter the values from the CMP and produce a quick result in mEq/L. This is the most frequently used calculation used in standard lab review.
Some clinicians use a version that includes potassium:
Anion gap = Sodium + Potassium − Chloride − Bicarbonate
However, the potassium-inclusive version is less commonly used in everyday lab interpretation. For most practical purposes, the potassium-free formula is the one people mean when they ask how to calculate the anion gap from CMP results.
The normal range can vary by laboratory because different analyzers and methods may produce slightly different values. That is why it is important to compare your number with the lab’s own reference range, rather than relying on a single universal cutoff. In general, the result is interpreted alongside the patient’s total acid-base status and clinical context.
When reviewing a result, remember that a normal anion gap does not always mean everything is fine, and an elevated value does not suggest one specific cause on its own. It is a medical calculator result that must be evaluated with other findings.
Detailed Demonstration Using CMP Results
Here’s a basic illustration using sample lab values from a CMP:
- Sodium = 140 mEq/L Chloride = 104 mEq/L CO2 = 24 mEq/L
Then use the calculation using direct formula substitution:
Anion gap = 140 − 104 − 24
The result is a figure of:
Anion gap = 12 mEq/L
This number would generally fall within many labs’ typical reference range, though the exact cutoff depends on the laboratory’s method and reporting style. To put it differently, the same number could be normal in one lab and borderline in another. This is why, the lab’s own reference anion gap clinical significance interval matters more than a generic estimate.
For result interpretation, you would contrast the calculated value with the lab’s listed range and then consider the rest of the CMP. If bicarbonate is low and the anion gap is elevated, that pattern may indicate an acid-related problem. If the value is normal, the issue could still involve another type of electrolyte imbalance, so the number is only one piece of the puzzle.
When you use an anion gap calculator, make sure the values are entered exactly as reported. A small input error can change the result enough to affect the interpretation of the blood chemistry.
What Is a Elevated Anion Gap Indicate?
A high anion gap often points toward excess unmeasured acids in the blood and is commonly associated with metabolic acid buildup. This is one of the main reasons the anion gap is so useful in everyday laboratory interpretation. It helps narrow the differential diagnosis when the body is in an acidotic state.
Frequent causes of a raised anion gap include:
- Lactic acid buildup — lactate accumulation, often from reduced oxygen delivery to tissues or other metabolic stress Ketone buildup — acid buildup related to ketosis, such as diabetic type, alcoholic, or starvation-related states Toxic alcohols — substances that can trigger a dangerous acid-base disturbance
These problems are important because they may require urgent evaluation. A elevated value does not confirm one diagnosis, but it signals a potential acid-base problem that deserves prompt attention. For that reason, the anion gap is a practical diagnostic clue rather than a standalone answer.
It also helps to review the bicarbonate result and the chloride level together. A low bicarbonate level with a elevated anion gap often strengthens concern for metabolic acidosis. The final judgment depends on the complete CMP, symptoms, and other lab findings.
What Does a Low Anion Gap Mean?
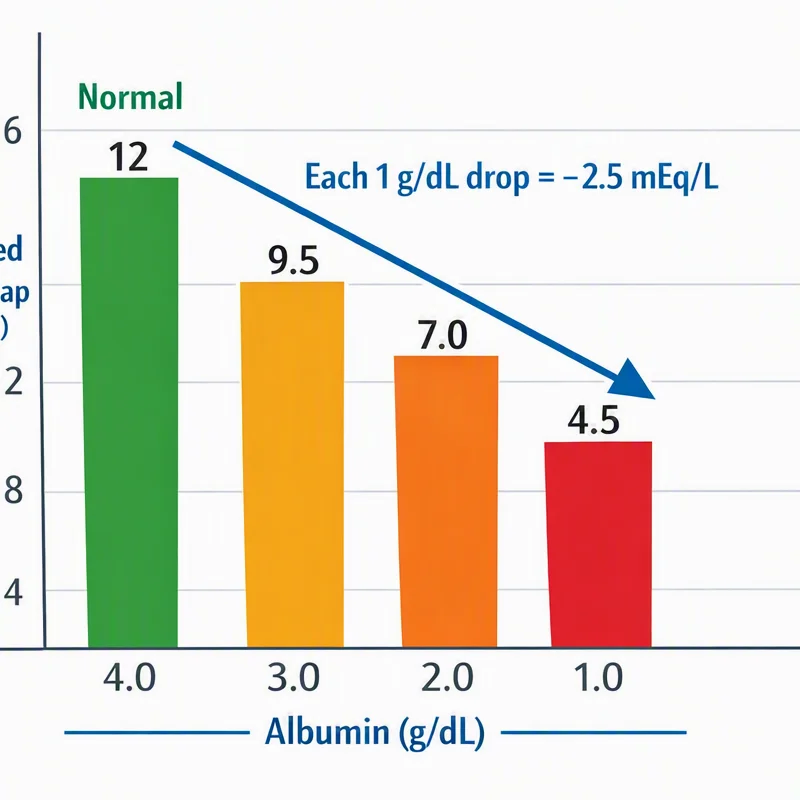
A low anion gap is uncommon, but it can still be clinically meaningful. One of the most common explanations is hypoalbuminemia, which means a reduced concentration of albumin in the blood. Because albumin is a negative-charge protein, reduced levels can reduce the measured gap.
Other potential causes of a low anion gap include:
- Paraproteinemia — extra abnormal proteins that can affect the calculation Lab error — a mistaken result or reporting issue Unusual shifts in sodium, chloride, or bicarbonate values
In many cases, a low value should lead to a careful check of the raw numbers and the lab report. Since the anion gap is derived from measured electrolyte values, a problem with one input can produce a false result. That is why a one low result should not be taken at face value without confirming the surrounding blood chemistry.
If albumin is low, the uncorrected result may minimize the true acid burden. That is where albumin correction becomes useful, especially when the clinical picture suggests a serious condition but the raw gap seems normal or low.
When to Use Corrected Anion Gap
The corrected anion gap is applied when serum albumin is abnormal, especially when hypoalbuminemia is present. Because albumin influences the usual gap, lower protein levels can hide an elevated acid load. That is why albumin correction is often used in the right clinical context.
A corrected value helps sharpen lab interpretation when the raw result seems less striking than expected. This is especially useful in patients who have low protein levels, where the uncorrected result may not fully capture the underlying acid-base status.
While correction formulas vary, the principle is consistent: if albumin is low, the observed gap should be adjusted upward to estimate what it would be with a typical albumin concentration. That adjusted estimate can better reveal a hidden high anion gap state.
Use the corrected approach when:
- Albumin is below the normal reference range The patient appears acidotic but the raw gap is not elevated There is concern that the CMP may be masking an important abnormality
The corrected number is not always needed, but it can make a major difference in interpretation. A smart use of the anion gap calculator includes knowing when the uncorrected result is not enough.
Frequent Errors When Calculating Anion Gap
While the formula is easy, a few common issues can alter the result. Focusing on details helps ensure precise calculation and better clinical significance.
- Incorrect units — verify all values are in the same unit, usually mEq/L Potassium add-in — do not add potassium unless you intentionally want the potassium-inclusive formula Entry error — transcribing the wrong sodium, chloride, or CO2 value can change the answer Reference ranges — always check the number with the correct lab-specific range
Another frequent problem is confusing CO2 with oxygen or a different unrelated value. In a CMP, CO2 generally reflects total carbon dioxide and is used as a proxy for bicarbonate in the formula. If you accidentally use the wrong line from the report, the final number will be wrong.
It is also essential not to ignore the overall pattern of the panel. An anion gap that looks abnormal may reflect a broader electrolyte imbalance, a data entry issue, or a transient physiologic change. Good lab interpretation depends on the whole picture, not just one calculated number.
FAQs About Anion Gap From CMP
How do you calculate anion gap from CMP results?
Take the CMP values for sodium, chloride, and CO2. The basic formula is sodium minus chloride minus bicarbonate, with CO2 used as the bicarbonate estimate in most panels. An anion gap calculator can do this quickly, but you can also calculate it by hand using the reported numbers from the comprehensive metabolic panel.
What’s the normal anion gap range?
The normal values depend on the lab’s method and reference range. Many labs consider the result normal within a fairly narrow interval, but there is no single universal cutoff. Always compare the number with the range printed on the report for accurate CMP interpretation.
Should potassium be added to the anion gap formula?
Generally, no. Most everyday calculations leave potassium out, even though a potassium-inclusive version exists. For standard medical testing evaluation, the simpler formula is the one most often used. If potassium is included, the result will be somewhat higher, so it https://anion-gap-chart157.novacrestiq.com/posts/calculating-anion-gap-in-mmol-l is important to know what formula is being applied.
What causes a high anion gap on a CMP?
A high result can suggest metabolic acidosis, especially from lactic acidosis, ketoacidosis, or exposure to toxic alcohols. It is a helpful diagnostic clue but not a diagnosis by itself. The rest of the CMP, symptoms, and clinical context help identify the cause.
Why would an anion gap be low on lab results?
A low value is often linked to hypoalbuminemia, since albumin affects the calculation. It can also occur with paraproteinemia or a lab error. If the result seems unexpected, examine the raw electrolyte values, verify the report, and consider whether albumin correction is needed for a better interpretation.