What the Anion Gap Measures
The anion gap is a practical way to read serum electrolytes and understand whether the body’s acid base balance may be disturbed. It is not a literal measurement of a single substance. Instead, it is a derived value that helps detect hidden ions in the blood when analyzing a standard electrolyte panel.
Clinically, the anion gap is commonly used to assess acid buildup. This is a metabolic disorder in which too much acid builds up or too much bicarbonate is lost. Because the calculation uses routine blood test results, it acts as a practical assessment tool in laboratory interpretation and clinical evaluation.
An Anion Gap Calculator helps users work out anion gap quickly and consistently, especially when they want anion gap with units properly shown. That matters because the value is only meaningful when the https://anion-gap-calculator659.lowescouponn.com/can-hyperproteinemia-affect-the-anion-gap reference ranges and context are understood correctly.
In basic terms, the anion gap reflects the relationship between positively charged and negatively charged particles in blood. The main electrolytes involved are sodium, chloride, and bicarbonate. When the balance shifts, the result can point toward an electrolyte imbalance, an acid-base disorder, or a more specific condition such as high anion gap metabolic acidosis.
Anion Gap Calculation & Estimation
The standard anion gap equation uses three standard serum measurements: sodium, chloride, and bicarbonate. The formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some laboratories may use a somewhat different version that includes potassium, but the most widely used clinical formula uses serum sodium, serum chloride, and serum bicarbonate. This is the formula most people expect from an Anion Gap Calculator.
To calculate anion gap one step at a time:
- Take the serum sodium value. Sum the serum chloride and serum bicarbonate values together. Deduct that total from sodium.
Example: if sodium is 140, chloride is 102, and bicarbonate is 24, the calculation is 140 − (102 + 24) = 14. This is the fundamental calculation, but interpretation depends on the units, the reference range, and whether albumin correction is needed.
Since anion gap is a computed number rather than a directly measured electrolyte, it should always be interpreted alongside the blood chemistry pattern. A apparently normal number does not always rule out disease, and an out-of-range result does not always mean a serious disorder without additional context.
Units Used in Anion Gap Calculation
Anion gap is commonly reported in mEq/L or mmol/L. In many cases, these values are usually numerically equivalent for the electrolytes used in the formula, which is why many clinicians and lab reports treat them similarly. However, users should always check the laboratory units shown on the report before making assumptions.
The calculation is based on serum chemistry, so the unit formatting follows how the laboratory measures the electrolytes. Sodium, chloride, and bicarbonate are often listed as either mEq/L or mmol/L, depending on the analyzer and reporting system.
For most routine interpretation, anion gap with units does not require conversion if all components come from the same lab report. Consistency is the key point. A calculator should use values from the same electrolyte panel and preserve the same units in the final answer.
Here are the practical takeaways:
- mEq/L is widely used in clinical chemistry reporting. mmol/L is also commonly used and often matches the numeric result. Mixed units can lead to confusion, especially if a value is copied incorrectly.
When using an Anion Gap Calculator, always check the units before reviewing the interpretation. Even though the formula is simple, the reliability of the result depends on accurate blood chemistry data and correct laboratory units.
Normal Anion Gap Range and Reference Values
The reference range for anion gap changes by laboratory because various analyzers and reference methods may produce slightly different results. For this reason you should use the lab’s lab range rather than a one universal number.
In many settings, the anion gap is viewed normal when it falls within a small range centered around the low teens, but the exact reference values vary. Some reports also adjust interpretation based on whether potassium is included in the formula. Because of these differences, the numeric result should routinely be compared with the local lab’s published values.
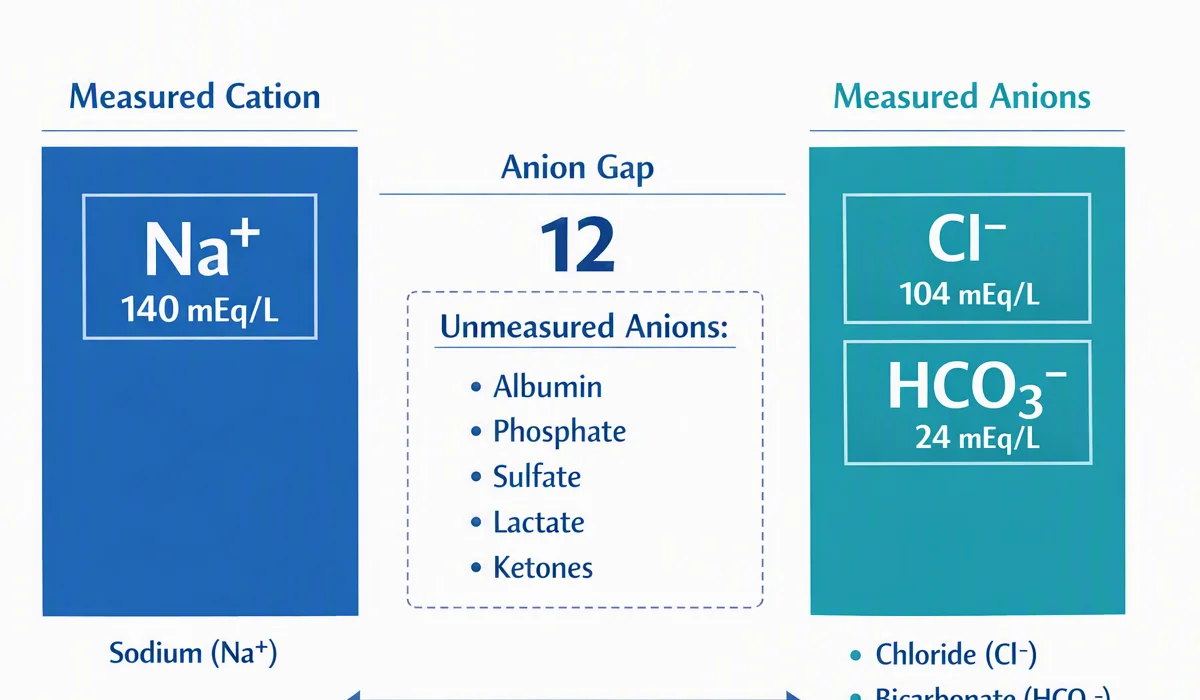
Albumin plays an key role in the normal range. Since albumin is a major unmeasured anion, a low albumin level can make the anion gap appear lower than expected. This is why albumin correction may be required when interpreting blood test results in patients with low albumin.
The corrected anion gap is often more informative than the raw number when albumin is reduced. This adjustment helps avoid missed recognition of an underlying acid-base disorder. If albumin is low, a apparently acceptable anion gap can mask a real abnormality.
These values should always be interpreted in context:
- Use the lab-specific published range. Check whether the result is uncorrected or corrected. Review albumin level before drawing conclusions.
High Anion Gap vs Normal Anion Gap Metabolic Acidosis
One of the primary uses of the anion gap is separating high anion gap metabolic acidosis from normal anion gap metabolic acidosis. Each are forms of metabolic acidosis, but they result from distinct mechanisms and therefore point to different causes.
In high anion gap metabolic acidosis, extra acids gather in the body. These acids are not directly measured in the routine electrolyte panel, so the anion gap widens. Common examples include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion.
In normal anion gap metabolic acidosis, bicarbonate is reduced and replaced by chloride, so the gap remains within the expected range. This is also called hyperchloremic metabolic acidosis. The acid-base balance is still abnormal, but the pattern is not the same as from high-gap states.
Lactic acidosis is a common cause of high anion gap metabolic acidosis. It can occur when tissues are not receiving enough oxygen or when metabolism is greatly stressed. Ketoacidosis is another classic cause, especially when the body produces too many ketones. Renal failure can also cause accumulation of acids because the kidneys cannot remove them properly.
By contrast, normal anion gap metabolic acidosis is often associated with bicarbonate loss from the gastrointestinal tract or kidneys. The chloride shift helps preserve electrical neutrality, so the gap may look normal even though the patient has a serious acid-base disorder.
Typical Causes of an Abnormal Anion Gap
An unexpected anion gap can indicate several significant clinical conditions, but the significance depends on whether the result is increased or reduced. For clinical practice, the most relevant abnormality is a raised result.
Ketoacidosis is a typical cause of elevated anion gap. This may develop in diabetes, starvation, or other metabolic states where ketone production goes up. These acids widen the gap because they add unmeasured anions to the bloodstream.
Kidney failure can also raise the anion gap by impairing acid excretion. As kidney function declines, acids collect, and the calculated gap increases.
Exposure to toxins is another key cause. Certain toxic substances create unmeasured acids or interfere with metabolism, leading to increased anion gap metabolic acidosis. In clinical evaluation, this possibility should be considered when the blood chemistry pattern is unexpected or severe.
Lactic acidosis is often seen in acute illness, poor tissue perfusion, or systemic stress. It is one of the key causes to identify quickly because it may reflect a severe underlying problem.
Bicarbonate loss is more often seen in non-anion gap metabolic acidosis. While the gap may not be elevated, the bicarbonate level is reduced, and the clinical impact can still be significant.
Additional causes and factors can include mixed acid-base disorders, medication effects, and changes in serum electrolytes. This is why an increased or low anion gap should never be interpreted in standalone fashion.
How to Interpret Results Correctly
Accurate interpretation involves more than checking a value against the reference range. A thorough clinical interpretation should account for albumin, the electrolyte pattern, and the possible acid-base disorder.
Initially, consider albumin correction if the patient has low albumin. Since albumin affects the anion gap, reduced levels can hide a clinically relevant elevation. The corrected anion gap offers a better estimate of the true acid-base status in many cases.
Then, look for a chloride shift. If bicarbonate is low and chloride is high, the pattern may indicate normal anion gap metabolic acidosis. This does not eliminate the possibility of illness; it just suggests a different mechanism than high-gap states.
Finally, connect the result with the broader acid-base disorder. The anion gap is one part of the story. It should be interpreted with pH, bicarbonate, clinical symptoms, and other relevant laboratory findings when available.
A useful approach is to think in layers:
- Is the anion gap high, normal, or low? Do sodium, chloride, and bicarbonate fit together logically? Is albumin decreased enough to warrant correction? Does the overall pattern fit the patient’s presentation?
That approach helps avoid common errors in interpretation. A result should reinforce the diagnosis, not substitute for clinical judgment.
When to Use an Anion Gap Calculator
An Anion Gap Calculator can be most useful if you have laboratory values from an electrolyte panel and want a quick, accurate way to calculate the anion gap. It is particularly useful during a medical assessment when rapid blood chemistry review is needed.
Rely on a calculator when reviewing lab values that include sodium, chloride, and bicarbonate. These measurements are usually available in a standard electrolyte panel and can be entered directly without calculation mistakes.
A calculator is also useful when comparing multiple sets of blood test results over time. Trend review can reveal whether the gap is rising, falling, or remaining stable. That can be helpful in monitoring treatment response or identifying a worsening metabolic disturbance.
In clinical workflows, the calculator serves as a practical support tool for laboratory interpretation. It can help clinicians, students, and patients understand the relationship between serum electrolytes and acid-base balance. It is not a substitute for professional diagnosis, but it can improve clarity when reviewing blood chemistry results.
It is especially helpful when:
- Evaluating possible metabolic acidosis Looking for high anion gap metabolic acidosis Assessing low albumin and considering albumin correction Reviewing an unexplained electrolyte imbalance
Frequently Asked Questions
What is the formula for calculating anion gap?
The standard formula is sodium minus the sum of chloride and bicarbonate. In equation form, it is anion gap = sodium − (chloride + bicarbonate). This is the most common formula used by an Anion Gap Calculator.
What units are used for anion gap?
Anion gap is commonly reported in mEq/L or mmol/L. In many cases, the numeric result is the same in both formats, but you should always follow the laboratory units shown on the report.
What is a normal anion gap range?
The normal range depends on the laboratory reference range and the testing method used. Always compare the result with the local reference values rather than assuming one universal normal range.
How does low albumin affect the anion gap?
Reduced albumin can decrease the observed anion gap because albumin is a key unmeasured anion. That is why albumin correction is important; the corrected anion gap may reveal an abnormality that the uncorrected value conceals.
What does a high anion gap indicate?
A high anion gap often points to high anion gap metabolic acidosis. Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion. The result should always be read with the full clinical picture and other blood test results.