What does the anion gap refer to?
The anion gap is a computed value used to gauge acid-base balance from a routine electrolyte panel or serum chemistry. It compares major checked cations and anions, usually based on sodium, chloride, and bicarbonate. Because not all charged particles are directly measured, the anion gap suggests the amount of unmeasured anions in the blood.
In its most common form, the calculation is:
Anion gap = sodium - (chloride + bicarbonate)
Some formulas include potassium, but many clinicians use the more straightforward version without it because potassium plays less to the final value. The key idea is that a rising gap can suggest a metabolic derangement caused by acids or other unmeasured substances.
Understanding the anion gap normal range matters because a value that looks “normal” may still be unreliable if albumin is low or if there are mixed disorders. That is why interpretation should always happen in clinical context, not in isolation.
Why sepsis affects the anion gap
Sepsis can affect the anion gap because it often causes metabolic acidosis, especially when oxygen delivery and utilization are compromised. In a shock state, tissues may not receive enough oxygen, leading to tissue hypoperfusion and increased anaerobic metabolism. This can raise acid production, especially lactic acidosis, which increases the gap.
When cells generate excess lactate, hydrogen ions accumulate and bicarbonate is consumed buffering the acid. The result is often a reduced bicarbonate level GOLD MARK causes and an anion gap elevation. In sepsis, this pattern is a helpful diagnostic clue because it may reflect occult hypoperfusion even before blood pressure becomes severely abnormal.
Sepsis also produces a broader inflammatory and metabolic response that can contribute to organ dysfunction. Kidney involvement, altered perfusion, and changes in acid handling may all influence the gap. In other words, the anion gap is not just about lactate; it is a window into the biochemical effects of critical illness.
How to determine and correct the anion gap
You can determine the anion gap manually, but an anion gap calculator is often useful for quick analysis and for minimizing arithmetic errors. The calculator typically uses sodium, chloride, and bicarbonate, and some tools allow you to include potassium. Even so, the number should always be evaluated alongside the patient’s overall acid–base picture.
One of the most important modifications is the corrected anion gap, also called the albumin-corrected gap. Because albumin is a major unmeasured anion, low albumin can make the gap appear falsely low or “normal.” In sepsis, hypoalbuminemia is common, so the uncorrected value may downplay the true burden of acids.
A practical approach is to:
- Examine the sodium, chloride, and bicarbonate values from the chemistry panel. Calculate the anion gap using a consistent formula. Check albumin and use an albumin-corrected gap if it is low. Compare the result with the blood gas and serum lactate.
Correction does not override clinical judgment. It simply increases accuracy when assessing whether the patient has hidden acid accumulation. In septic patients, this step can help prevent a missed diagnosis of ongoing acid generation.
High anion gap versus expected-range anion gap in sepsis
During sepsis, a elevated anion gap metabolic acidosis often indicates buildup of organic acids, especially lactate. This is the typical pattern when tissue oxygen delivery is impaired. Yet, sepsis can also present with normal anion gap metabolic acidosis, particularly when bicarbonate is lost or when chloride rises relative to bicarbonate after large-volume fluid resuscitation.
That separation is important because a normal gap does not rule out significant illness. A patient may still have acidemia, elevated lactate, or impaired perfusion even if the calculated gap stays within the expected range. Mixed disorders are common in critical illness, so a “normal” result may mask concurrent problems.
Lactate is often the leading driver of a high gap in sepsis, but it is not the only one. If the patient has kidney injury, acids can accumulate because renal clearance is reduced. This can further increase the gap or complicate the pattern seen on the blood gas.
Think of the anion gap as a clue to the type of acidosis:
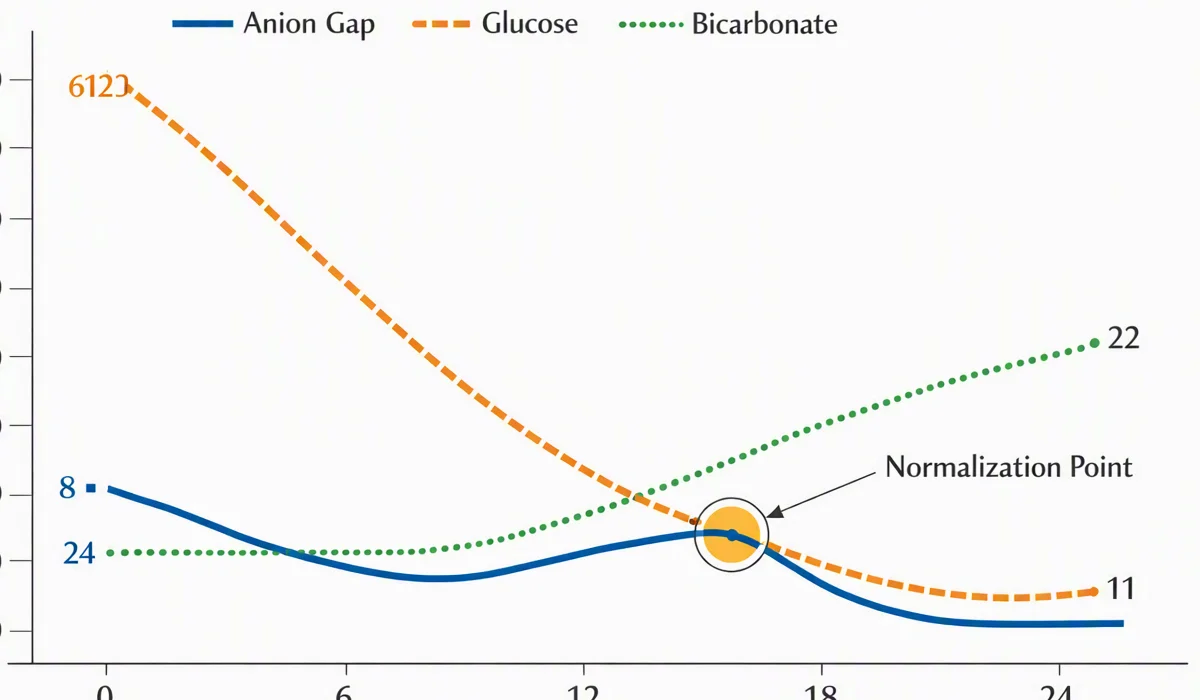
- High anion gap metabolic acidosis suggests unmeasured acids such as lactate or ketones. Normal anion gap metabolic acidosis suggests bicarbonate loss, chloride gain, or mixed physiology.
In sepsis, both patterns may occur over time as the patient’s perfusion, kidney function, and treatment response evolve.
Typical causes for high anion gap in septic patients
The primary cause of an high gap in sepsis is lactate from an excess of lactic acid. This may stem from tissue hypoperfusion, microcirculatory dysfunction, or impaired oxygen utilization. Still an elevated anion gap should not be assumed to be lactate alone.
Other key causes include:
- Ketone-related acidosis, particularly if the patient has diabetes, poor intake, or severe stress physiology. Kidney failure, which reduces acid excretion and allows unmeasured anions to accumulate. Poisonous alcohols, such as methanol or ethylene glycol, which are less common but high-risk and should be considered when the story does not fit sepsis alone.
These alternatives matter because sepsis can coexist with other metabolic problems. A patient may have infection plus ketoacidosis, or sepsis plus renal failure. It should therefore prompt a broader differential rather than a single-track conclusion.
If the anion gap is rising and lactate is not very high, clinicians should consider whether another process is contributing. For that reason serial assessment is more useful than a single isolated number.
How to interpret the findings: what this value can and cannot show
The anion gap is best used as a clinical pointer, not a diagnosis. It can suggest the presence of an acid–base imbalance, but it does not reveal the exact cause by itself. In sepsis, this is especially important because multiple processes can overlap at once.
A high gap may reflect accumulating unmeasured acids, but the number alone cannot tell you whether the cause is lactate, ketoacidosis, renal failure, or a toxin. Likewise, a normal gap does not exclude clinically important illness. That is why the anion gap must be paired with a blood gas analysis, lactate level, kidney function, and the overall exam.
One useful way to assess the number is to ask three questions:
- Is there acidemia on the blood gas? Is the gap value elevated after considering albumin? Does the pattern fit the patient’s clinical context and perfusion status?
If the answer is yes to all three, the concern for clinically significant acid accumulation is higher. If there is a mismatch, think about mixed acid-base disease, laboratory timing issues, or a non-lactate cause of metabolic derangement.
In short, the number does not replace bedside assessment. It reinforces or reduces a hypothesis about what is happening physiologically.
When to repeat testing and assess severity
For patients with sepsis, repeat testing is often more revealing than a single snapshot. Lactate over time levels help show whether the patient is reducing lactate or ongoing lactate production is present. Likewise, rechecking electrolytes can show whether the anion gap is improving, unchanged, or getting worse.
Providers also assess base deficit on the blood gas as a further indicator of metabolic burden. A worsening base deficit may support ongoing acidosis even if the gap has not yet changed dramatically. Together, these values can help with severity assessment and therapeutic response.
Follow-up labs are particularly helpful when:
- Lactate is elevated initially and you want to follow lactate clearance. There is worry for persistent tissue perfusion problems. Organ function is worsening or suspected kidney failure. The initial anion gap and blood gas fail to match the clinical picture.
Following the trend can uncover restored perfusion after resuscitation or an occult decline that requires escalation. In critical illness, the trend often carries more weight than the single value.
Common questions on anion gap during sepsis
What can anion gap indicate in sepsis?
During sepsis, the anion gap helps identify whether there is an acid-base imbalance from unmeasured acids circulating in the blood. An elevated gap can suggest lactic acidosis because of tissue hypoperfusion, but it may also reflect ketoacidosis, renal failure, or toxic alcohol exposure. It is a useful clue, not a standalone diagnosis.
Can sepsis cause a normal anion gap?
Yes. Sepsis can cause a normal anion gap metabolic acidosis, especially when bicarbonate is lost or chloride rises during fluid treatment. A normal anion gap does not rule out serious illness, elevated lactate, or poor perfusion. Mixed acid-base disorders are common in sepsis.
Why is it important to correct the anion gap for albumin?
Albumin is a major unmeasured anion, so low albumin can make the measured anion gap look deceptively normal. Correcting for albumin gives a better estimate of the true acid burden. This is especially important in critical illness, where hypoalbuminemia is common.
Does a high anion gap necessarily mean lactic acidosis in sepsis?
No, it does not. Lactic acidosis is common, but a high anion gap can also come from ketoacidosis, renal failure, or toxic alcohols. The anion gap should always be interpreted with the blood gas, serum lactate, albumin, and the rest of the clinical context.
When ought an anion gap be repeated in a septic patient?
Repeat it when you are monitoring response to treatment, especially if lactate is elevated, perfusion is uncertain, or the patient’s condition is changing. Trending the anion gap with serial lactate, electrolytes, and base deficit helps show whether the metabolic derangement is improving or worsening.