An anion gap calculator is more informative than a simple calculation tool when you need fast, reliable diagnostic interpretation of serum electrolytes. In clinical practice, the anion gap helps clinicians evaluate acid-base balance, check for metabolic acidosis, and focus a broad differential diagnosis by identifying likely causes of unmeasured anions from disorders driven by primary bicarbonate loss or chloride retention. Used well, it becomes part of a broader diagnostic algorithm rather than a stand-alone result.
This guide covers how the anion gap formula works, how to interpret a normal anion gap versus an elevated anion gap, and how to adjust for hypoalbuminemia using albumin correction. It also shows how to connect the result to real-world causes such as lactic acidosis, ketoacidosis, renal failure, renal tubular acidosis, and toxic alcohol ingestion.
How the Anion Gap Measures
The anion gap is a calculated value derived from common electrolytes on a basic metabolic panel. It measures the difference between measured positively charged ions and measured negatively charged ions, helping clinicians detect the presence of unmeasured anions in the blood. Since the body maintains tight acid-base balance through buffer systems and kidney function, changes in the gap can indicate a meaningful metabolic derangement.
In the classic interpretation, sodium is compared against chloride and bicarbonate, which are the main contributors in routine chemistry testing. The gap reflects the balance between these measured ions and other charged particles not directly reported, such as proteins, phosphate, sulfate, lactate, and organic acids. This is why the gap can reveal a hidden acid-base disorder even before the precise cause is known.
The test is often used as part of clinical assessment when a patient presents with low bicarbonate, altered mental status, unexplained tachypnea, or an abnormal metabolic profile. A single number does not confirm the diagnosis, but it can quickly guide attention toward the right branch of the differential diagnosis.
Anion Gap Formula and Required Inputs
The usual anion gap equation is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some medical professionals add potassium in the calculation, particularly in older references or some calculation approaches:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
Most modern clinical use prioritizes the sodium-based version because potassium is usually low relative to sodium and adds limited value to routine interpretation. Even so, an anion gap calculator may use either approach, so it is important to know which formula is being applied. Small differences in the equation can shift the number enough to affect clinical decision-making.
Key inputs are drawn from the electrolyte panel or chemistry panel: sodium, chloride, and bicarbonate. In many cases, the calculator also asks for albumin because low protein levels can mask a clinically important elevation. Since serum albumin level strongly influences the baseline gap, a raw number without context can be misleading.
For instance, a patient with sodium 140, chloride 104, and bicarbonate 24 has an anion gap of 12. That value may be normal depending on the lab’s reference range, but the interpretation changes if the patient has severe hypoalbuminemia or evidence of metabolic acidosis. The calculation is only the starting point for result interpretation.
How to Interpret a Typical vs Increased Anion Gap
Assessment starts with the lab’s reference range, since typical readings vary slightly by assay and institution. In general, a normal anion gap suggests that the bicarbonate decrease is being offset by a rise in chloride, while an elevated anion gap indicates accumulation of unmeasured acids or their anions. Both findings can indicate metabolic acidosis, but they reflect different etiologies.
A high anion gap metabolic acidosis usually means acid is being added to the body or retained because the kidneys cannot clear it effectively. Common causes include organic acids and toxins. By contrast, a normal anion gap metabolic acidosis is often a hyperchloremic process, where bicarbonate is lost and chloride rises to maintain electroneutrality.
Practical interpretation works best as a branching diagnostic algorithm:
- Normal anion gap: think bicarbonate loss or renal acid-handling problems. Elevated anion gap: think added acids, accumulation of acids, or toxin exposure. If the number seems unexpectedly normal, check albumin and consider anion gap correction.
It is important as well to verify whether the patient truly has metabolic acidosis. Low bicarbonate levels on a chemistry panel is not sufficient on its own; an arterial blood gas can clarify pH and breathing compensation. This is especially valuable when mixed acid-base disorders are possible.
Adjusted Anion Gap for Low Albumin
Albumin is a key unmeasured anion, so reduced albumin lowers the measured anion gap. That means a patient with hypoalbuminemia may have a deceptively normal or only slightly elevated result despite important acidosis. This is why albumin correction is important in standard interpretation.
The corrected anion gap raises the measured value upward when serum albumin is below normal. Several correction methods exist, but a common clinical approach is to add a fixed amount for each gram per deciliter albumin is below normal. The exact factor may change by institution, so the calculator should be used in line with local practice or its stated assumptions.
This anion gap correction is especially valuable in critically ill patients, patients with malnutrition, liver disease, chronic inflammation, or nephrotic states. In these settings, the raw number may diminish the burden of unmeasured anions and therefore hide a true acid-base disorder.
Consider this clinical logic: a patient has low bicarbonate and a “normal” gap, but the serum albumin level is markedly reduced. After albumin correction, the gap becomes elevated, revealing a mixed picture or a hidden high-gap process. In other words, the corrected number can alter the differential diagnosis and the speed of workup.
Clinical Differential of High Anion Gap Metabolic Acidosis
high anion gap metabolic acidosis happens when acids build up or are retained. In essence, bicarbonate is consumed while the accompanying anions are not captured in the standard panel. The outcome is a widened gap and a targeted differential.
Typical causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each one has distinctive clinical clues, but duplication is often seen, so the anion gap should be combined with patient history, physical exam, and lab values.
- Lactic acidosis: often related to hypoperfusion, sepsis, hypoxemia, or severe metabolic stress. Ketoacidosis: includes starvation ketosis, alcoholic ketosis, and diabetic ketoacidosis, which often presents with hyperglycemia, dehydration, and ketones. Renal failure: reduced acid excretion leads to build-up of acids and gradual metabolic derangement. Toxic alcohol ingestion: such as methanol or ethylene glycol, which can produce severe high-gap acidosis and end-organ injury.
Within DKA, the gap is commonly markedly raised because ketone bodies build up. In renal failure, the pattern may evolve with increasing retained acids and a decline in renal filtration. With toxic alcohol intake, the anion gap can increase early, and the clinical picture may include osmolar gap shifts, visual symptoms, neurologic impairment, or kidney injury depending on the agent.
By using an anion gap calculator in this context helps prioritize the next step in clinical assessment: lactate testing, ketone assessment, toxicology evaluation, or renal assessment. The value does not replace medical judgment, but it refines the differential assessment.
Diagnostic Overview of Normal Anion Gap Metabolic Acidosis
A normal anion gap metabolic acidosis is often called hyperchloremic acidosis because chloride rises as bicarbonate falls. In this setting, the issue is usually not the addition of unmeasured acid, but rather bicarbonate loss or impaired renal acid handling. The anion gap remains normal because chloride substitutes for the lost bicarbonate.
Common causes include diarrhea and renal tubular acidosis. Gastrointestinal bicarbonate loss is a classic mechanism in DKA anion gap closure diarrhea, especially when losses are prolonged or severe. The kidneys may also fail to acidify urine properly in renal tubular acidosis, producing a chronic or recurrent normal-gap acidosis.
Additional causes of normal anion gap metabolic acidosis can include high-volume saline administration, certain medications, and tubular dysfunction, but the main clinical distinction remains the same: chloride increases as bicarbonate falls. This is why the serum chemistry pattern matters as much as the calculated number.
When faced with a normal-gap pattern, ask whether the problem is a true loss of alkali. If the answer is yes, then bicarbonate loss from the gut or kidney becomes central to the diagnostic workup. That makes the anion gap an efficient tool for directing the next branch of the acid-base differential diagnosis.
Common Interpretation Issues and Clinical Context
Even when a careful calculation can be misleading if the clinical setting is overlooked. One common issue is lab error, such as contaminated specimen, data entry error, or a discordant set of results. Before deciding that a major acid-base problem is present, check that the lab values are internally consistent and compatible with the patient’s presentation.
A further mistake is missing albumin. If the serum protein level is reduced, the raw anion gap may underestimate the true burden of unmeasured anions. For this reason albumin correction should be considered in any patient with suspected metabolic acidosis and low albumin.
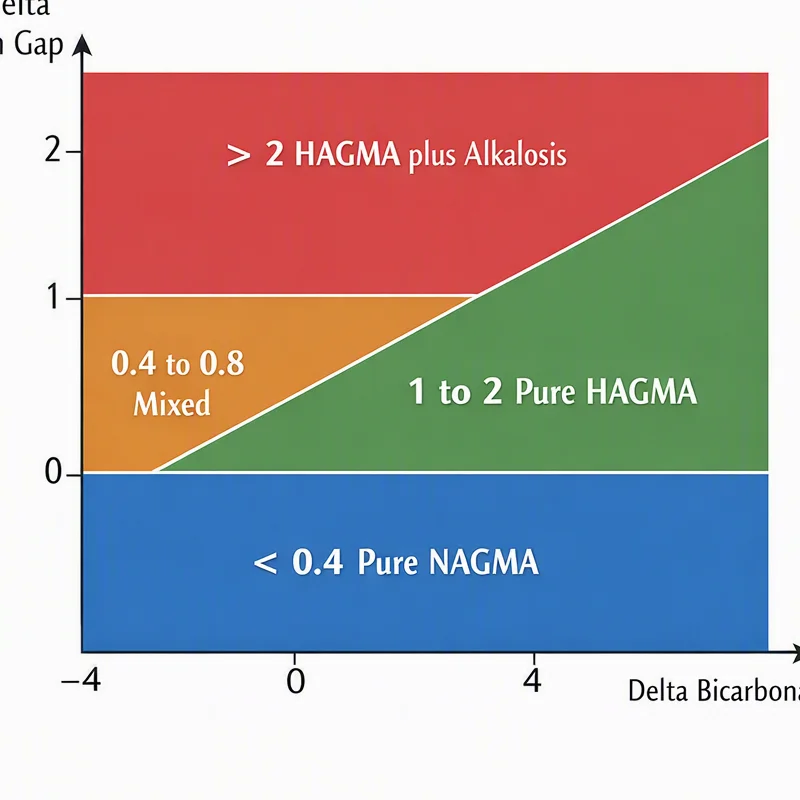
The delta gap is another important concept. When the anion gap is high, the delta gap compares the rise in the gap to the fall in bicarbonate. This helps detect mixed acid-base disorders, such as simultaneous metabolic alkalosis or an additional normal-gap acidosis. In practice, the delta gap can reveal whether the patient’s metabolic profile is more complicated than the first calculation suggests.
Other common mistakes include using the wrong reference range, failing to check pH on an arterial blood gas, and interpreting a single number without considering respiratory compensation. The best results come from integrating the calculator output with a full clinical assessment and the broader picture of electrolyte imbalance and organ function.
When You Should Use an Anion Gap Calculator in Clinical Workflow
An anion gap calculator is most helpful early in the evaluation of suspected acid-base disorder. It fits naturally into a workflow that begins with a basic metabolic panel or electrolyte panel, then progresses to an arterial blood gas when pH and compensation need clarification. This sequence enables efficient clinical decision support and more focused testing.
Use the calculator for low bicarbonate levels, when there is unexplained tachypnea or altered mental status, or when there is concern for toxin exposure, sepsis, renal anion gap clinical significance dysfunction, or ketoacidosis. It is also useful when reviewing serial labs because changes in the anion gap can reflect improvement or worsening in the underlying metabolic derangement.
In practical terms, the workflow often looks like this:
- Examine the basic metabolic panel for sodium, chloride, and bicarbonate. Perform the anion gap calculation using the calculator. Measure albumin and apply corrected anion gap logic if needed. Order an arterial blood gas to confirm acidemia or alkalemia and assess compensation. Branch to the appropriate differential diagnosis for high-gap or normal-gap causes.
This approach makes the calculator part of a broader clinical decision-making process rather than a standalone number generator. It helps clinicians advance efficiently from a chemistry abnormality to a meaningful explanation, especially in high-acuity settings.
FAQ About Anion Gap Interpretation
What is an anion gap calculator used for?
An anion gap calculator is used to determine the difference between measured cations and anions on a chemistry panel. Clinically, it helps identify metabolic acidosis, support acid-base differential diagnosis, and differentiate between high-gap and normal-gap causes of acid-base disorders. It is especially helpful when combined with albumin and arterial blood gas data.
How do you calculate the anion gap?
The most common anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). Some methods also include potassium, but the sodium-based formula is most commonly used. The values usually come from a basic metabolic panel or related electrolyte panel.
Why does low albumin affect the anion gap?
Albumin is a key unmeasured anion, so when hypoalbuminemia is present, the measured gap can appear lower than it truly is. For that reason albumin correction is important. A corrected anion gap better reflects the real burden of unmeasured acids and improves diagnostic interpretation.
What leads to a high anion gap metabolic acidosis?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, diabetic ketoacidosis, renal failure, and toxic alcohol ingestion. These conditions increase unmeasured acids or decrease acid clearance, expanding the gap and signaling a significant metabolic problem.
Can a normal anion gap still occur with metabolic acidosis?
Yes. A patient can have normal anion gap metabolic acidosis, also called hyperchloremic acidosis. This pattern often occurs with diarrhea or renal tubular acidosis, where bicarbonate loss is matched by a rise in chloride. In that setting, the gap stays normal even though true acidosis is present.