What Is the Anion Gap?
The anion gap is a way to examine your electrolytes on a blood test and determine whether the body may have an acid-base balance problem. It is not a direct measurement of a single substance. Instead, it reflects the difference between measured ions in the blood, which can help reveal the presence of unmeasured anions that are not listed on a standard lab report.
Clinically, the anion gap is a useful diagnostic tool because it helps clarify the cause of an acid-base disorder. When the body generates too much acid, is missing base, or cannot clear acids properly, the result may show up as an abnormal anion gap. That is why an anion gap calculator can be helpful when interpreting blood chemistry and lab values from a basic metabolic panel.
The test is commonly interpreted alongside the rest of the serum electrolytes, since the result is easiest to interpret in clinical interpretation. A normal number does not always mean everything is fine, and an abnormal number does not automatically give a diagnosis. It is one clue among several, including symptoms, history, and other lab findings.
In simple terms, the anion gap helps answer a basic question: are there hidden acids or other charged particles in the blood that are not being counted directly? That question matters in many forms of metabolic acidosis and other types of electrolyte imbalance.
How to Calculate Anion Gap from a BMP
A standard metabolic panel, often abbreviated as BMP, generally provides the key numbers needed for an anion gap calculation formula. The three main values are sodium, chloride, and bicarbonate. In many labs, bicarbonate may appear as carbon dioxide or CO2, which is used as a practical stand-in for bicarbonate in the blood test.
The most common formula is:
Anion gap = sodium − (chloride + bicarbonate)
Using a calculator makes this easy, but it is also simple to do by hand. For example, if sodium is 140, chloride is 104, and bicarbonate is 24, the calculation is:
140 − (104 + 24) = 12
That result would often fall within a typical expected range, depending on the laboratory’s method and reference values.
Some labs and clinicians also look at a modified version that includes potassium, but the sodium-based approach is the most common and is usually what people mean when they refer to an anion gap calculator. Because lab methods differ, the exact number can vary slightly from one lab panel to another. What matters most is how the number fits the overall clinical picture.
It is important to remember that bicarbonate on a BMP may be reported as total CO2. Even though the label says carbon dioxide, the value is generally used in the same way for anion gap calculation. Understanding that detail helps prevent confusion when reviewing the result.
Typical Anion Gap Range
The normal range for anion gap depends on the laboratory, the instrument used, and whether potassium is included. Many labs use a range about around 8 to 12 or 12 to 16, but there is no one universal value. This is why the same result may be considered normal in one setting and slightly abnormal in another.
Method variation is a major reason for differences in interpretation. The chemistry technique, calibration, and reporting style can shift the expected range. Because of that, a calculator should be used as a guide, not as a standalone diagnosis.
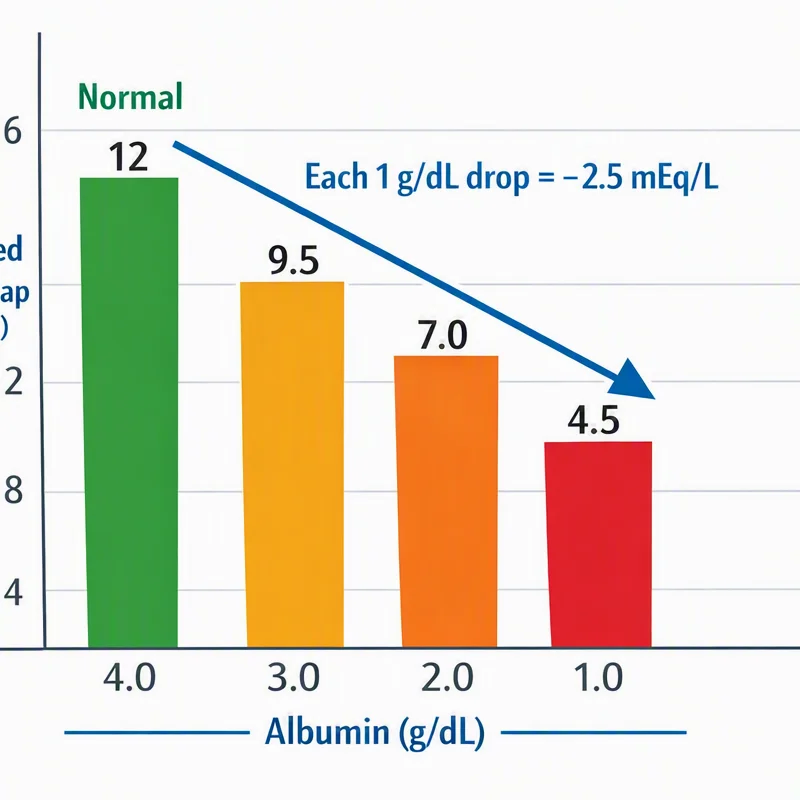
Serum albumin also matters because it is a major negatively charged protein in the blood and has a strong effect on the anion gap. If albumin is low, the apparent anion gap may look lower than expected even when there is an acid-base problem. That is why many clinicians review albumin alongside the BMP.
A normal anion gap does not rule out every disease. It simply suggests that the measured ions on the BMP do not show a large excess urine anion gap formula clinical of unmeasured acids. In contrast, a high anion gap or low anion gap may point toward a specific set of causes that deserve more attention.
Elevated Anion Gap Reasons
A high anion gap commonly raises concern for metabolic acidosis. In other words the body has too much acid, or it is not getting rid of acid efficiently. The extra acid is often not directly listed on the BMP, and this is why the gap increases.
One common cause is lactate buildup, which can happen when tissues do not get enough oxygen, when the body is under major stress, or when certain medical conditions interfere with normal metabolism. In this situation, lactate accumulates and adds to the gap.
Another major cause is ketone buildup. This can occur when the body breaks down fat too quickly and produces ketones. It is often discussed in relation to diabetes, alcohol use, or prolonged poor intake. Ketones are unmeasured anions, so they can raise the anion gap significantly.
Renal failure is another important cause. When the kidneys cannot clear acids efficiently, acidic waste products collect in the blood. The result may be a higher anion gap and a pattern consistent with acid retention.
Other causes can include toxins, certain medications, and less common metabolic disorders. However, the most practical approach is to use the anion gap as a screening test that indicates an underlying cause rather than as a final answer. The next step is always to interpret the result with symptoms, history, and the rest of the blood chemistry.
In general, a rising anion gap signals a worsening acid burden or a change in the body’s chemistry that needs timely evaluation. A high value does not tell the whole story, but it can be a strong clue that something is wrong with the body’s acid-base balance.
Low Anion Gap Causes
A low anion gap is not as common than a high one, but it can still be medically important. One major reason is hypoalbuminemia, which means the blood albumin level is low. Since albumin is a negative-charged protein, a decreased protein level can reduce the measured gap.
Paraproteinemia is another possible cause. This means abnormal proteins in the blood, often seen in certain plasma cell disorders. These proteins can alter the balance of charges in blood and affect the anion gap result.
Lithium can also result in a low anion gap in some cases. Because lithium is a positively charged ion, it can alter the relationship between measured cations and anions on lab testing. This is one reason medication review matters when evaluating lab values.
Sometimes a low result is due to a lab issue, sample problem, or an unusual set of electrolytes rather than a disease. That is why the result should always be checked against the rest of the clinical picture. A low number can be a clue, but it should not be interpreted in isolation.
When the anion gap is low, clinicians often think about albumin, abnormal proteins, medication exposure, and the possibility of an error in the sample or reporting process. The result may not be urgent by itself, but it can reveal a meaningful underlying condition.
How The albumin level Affects the Anion Gap
Correction for albumin is a very important ideas in interpreting the anion gap. As albumin bears a negative charge, it contributes to the normal anion gap. If albumin is low, the gap may appear falsely low even though the patient may still have an acid-base problem.
This happens because albumin is part of the body’s protein binding system and acts as a major unmeasured anion. When the protein level changes, the balance of measured and unmeasured ions shifts as well. That is why many clinicians use a correction formula to estimate the corrected anion gap.
A common correction approach adjusts the gap upward when albumin is below normal. The exact formula can vary by source, but the core idea is the same: lower albumin should prompt a higher corrected value than the raw calculation suggests. This helps prevent failing to detect a true metabolic acidosis.
For example, if a person has a seemingly normal anion gap but also has significantly low albumin, the adjusted result may reveal that the gap is actually abnormal after correction. That is why albumin is so important in clinical interpretation. It enhances the accuracy of the result and reduces the risk of overlooking an underlying problem.
In practical terms, whenever albumin is low, the raw anion gap should be viewed cautiously. The corrected result often provides a better estimate of the real acid-base status and helps guide the next step in evaluation.
Anion Gap Calculator Examples
Viewing a few example calculation cases can make for the process more straightforward. The following cases use typical BMP values and show how the result affects the assessment.
Example 1: Sodium 138, chloride 102, bicarbonate 24.
Anion gap = 138 − (102 + 24) = 12.
This would often be considered within the expected normal range, depending on the lab. If the person has no alarming symptoms and the rest of the blood chemistry is stable, the result may simply be normal.
Example 2: Sodium 140, chloride 100, bicarbonate 14.
Anion gap = 140 − (100 + 14) = 26.
This is a elevated anion gap result. In the right clinical situation, it may suggest lactic acidosis, ketoacidosis, or another cause of acid buildup. The next step would be to look for the underlying cause and assess whether the patient needs immediate treatment.
Example 3: Sodium 136, chloride 108, bicarbonate 28.
Anion gap = 136 − (108 + 28) = 0.
This is a markedly low result and should prompt review of albumin, medications, and the possibility of lab error. If albumin is low, a albumin-corrected anion gap may look different after adjustment.
This shows why an anion gap calculator is useful. It quickly turns raw blood test numbers into a more meaningful pattern. Still, the result should always be interpreted with the full clinical picture, not just the formula alone.
When It Is Time to Seek Medical Evaluation
An unexpected anion gap should be viewed in light of symptoms and overall illness severity. If someone has disorientation, nausea and vomiting, severe weakness, increased breathing rate, dehydration, chest pain, or major changes in alertness, medical evaluation may be needed as soon as possible. Those symptoms can occur with serious acid-base problems and may need urgent attention.
It is especially important not to ignore a high anion gap when it appears with signs of illness. A result suggesting metabolic acidosis can suggest conditions such as lactic acidosis, ketoacidosis, or renal failure, all of which may require timely treatment depending on the situation.
A low anion gap is often less dramatic, but it still deserves attention if it is repeated or unexplained. Conditions like hypoalbuminemia or paraproteinemia may warrant additional testing. Medication exposure, including lithium, should also be reviewed when relevant.
Most importantly, the lab result should never be considered without clinical context. The same number can mean quite different information depending on age, symptoms, medical history, and the rest of the blood chemistry. If the result is unexpected, asking a clinician to review the full picture is the best approach.
FAQ About Anion Gap and BMPs
What exactly is an anion gap calculator used for?
An anion gap calculator is used to estimate the anion gap from a basic metabolic panel or BMP. It helps with medical interpretation by showing whether the blood has a pattern that suggests hidden acids or another type of electrolyte imbalance. It is a helpful screening test, but it does not take the place of full clinical evaluation.
How do you calculate anion gap from a basic metabolic panel?
Use the calculation formula: sodium minus the sum of chloride and bicarbonate. In other words, anion gap = sodium − (chloride + bicarbonate). On some reports, bicarbonate may be listed as carbon dioxide. This is why reading the lab values carefully matters when doing the anion gap calculation.
What is a high anion gap?
A increased anion gap commonly indicates metabolic acidosis. Frequent causes are lactic acidosis, ketoacidosis, and renal failure. The result points to excess unmeasured anions in the blood and should be considered alongside symptoms and other lab findings.
Can hypoalbuminemia alter the anion gap?
Yes, it can. Albumin has a significant influence on the anion gap because it is a negatively charged protein in the blood. Hypoalbuminemia can make the raw number appear lower than it truly is. That is why albumin correction and the corrected anion gap are important in some cases.
Is an abnormal anion gap always an emergency?
No, it is not always urgent. Some abnormal results are mild or explained by known conditions, and others are discovered incidentally on routine blood test review. However, if the abnormality comes with significant symptoms or suggests a serious acid-base problem, it may need prompt attention. The best approach is to consider the full clinical context and ask a clinician to review the result.