This anion gap is a calculated value that helps clinicians evaluate a child’s electrolyte balance and overall acid-base balance. If you’re using an Anion Gap Calculator, the main question is usually whether the result falls within the expected normal range for children. Typically, the answer depends on the laboratory’s reference range, the child’s age, and the rest of the blood test results.
For many pediatric lab tests, a typical anion gap is often considered to be around 8 to 16 mEq/L when albumin is normal, but the exact normal laboratory range can differ by method and institution. Because the result is tied to local laboratory values, it is best interpreted with the child’s serum chemistry panel and overall symptoms in mind.
What’s the Anion Gap?
The anion gap is a calculated estimate of the difference between recorded positive and negative charges in the blood. It is not directly measured on its own. Instead, it is derived from electrolytes routinely included on a serum chemistry panel, especially sodium, chloride, and bicarbonate.
Put simply, the anion gap helps clinicians search for hidden acids in the bloodstream. Because routine lab testing does not measure every charged particle, this calculated value offers useful insight into acid-base disorder patterns. It is especially helpful when trying to identify a metabolic disturbance in a child.
The usual version of the anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Some laboratories may use slightly different formulas or include potassium, so the number can change a little depending on the method. That is why the local reference range matters so much for medical interpretation.
When the value is normal, it generally indicates that the balance between measured cations and anions is expected. When it is abnormal, it can signal an underlying cause that requires more evaluation.
Normal Anion Gap Range in Children
The usual range for the anion gap in kids is usually similar to adults, but the exact laboratory range depends on the laboratory, the test method, and the child’s age. In numerous settings, a common pediatric range is roughly 8 to 16 mEq/L when potassium is not included. A few labs use a slightly narrower or wider range.
Because children grow and their physiology changes, the age-based range may differ across age groups, especially in newborns and infants. For that reason, clinicians rely on the lab’s posted reported values rather than a universal number.
A child’s result should also be viewed alongside serum sodium, serum chloride, and serum bicarbonate, since these numbers shape the final calculation. A result that looks mildly abnormal on paper may still be expected in a specific diagnostic context.
Important things to note:
- The normal range can vary by laboratory. Age may matter, especially in younger children. Albumin levels can affect the result. A single abnormal result is not always clinically significant.
Practically speaking, the anion gap is one piece of the overall assessment. The most useful interpretation comes from combining the number with the child’s symptoms, exam findings, and other blood chemistry results.
How an Anion Gap Calculator Works
An Anion Gap Calculator employs the anion gap formula to determine the value from a child’s lab values. The calculator usually requests sodium, chloride, and bicarbonate, which are part of a standard serum chemistry panel.
This is the basic procedure:
- Input the child’s serum sodium. Enter the serum chloride. Enter the serum bicarbonate. The tool subtracts chloride and bicarbonate from sodium. The result is the calculated anion gap.
This calculation assists determine whether the child may have an abnormal result related to an acid-base balance disorder. If the gap is high, clinicians often consider causes of metabolic acidosis. If it is low, they check for issues such as low albumin, hypoalbuminemia, or a possible lab error.
Because the calculator relies on blood chemistry, it reflects the accuracy of the inputs. Small changes in bicarbonate or chloride can alter the final number. That is why a blood test should always be reviewed in context, not in isolation.
The calculator is useful for quick screening, but it does not take the place of professional medical interpretation. It is best employed as a tool to assist decision-making, not as a stand-alone diagnosis.
What Can Cause a High Anion Gap in Children?
A high anion gap often indicates there are extra acids in the blood that are not being directly measured in the basic chemistry panel. In children, the most common concern is metabolic acidosis. This pattern suggests that the body is generating or holding on to acids faster than it can remove them.
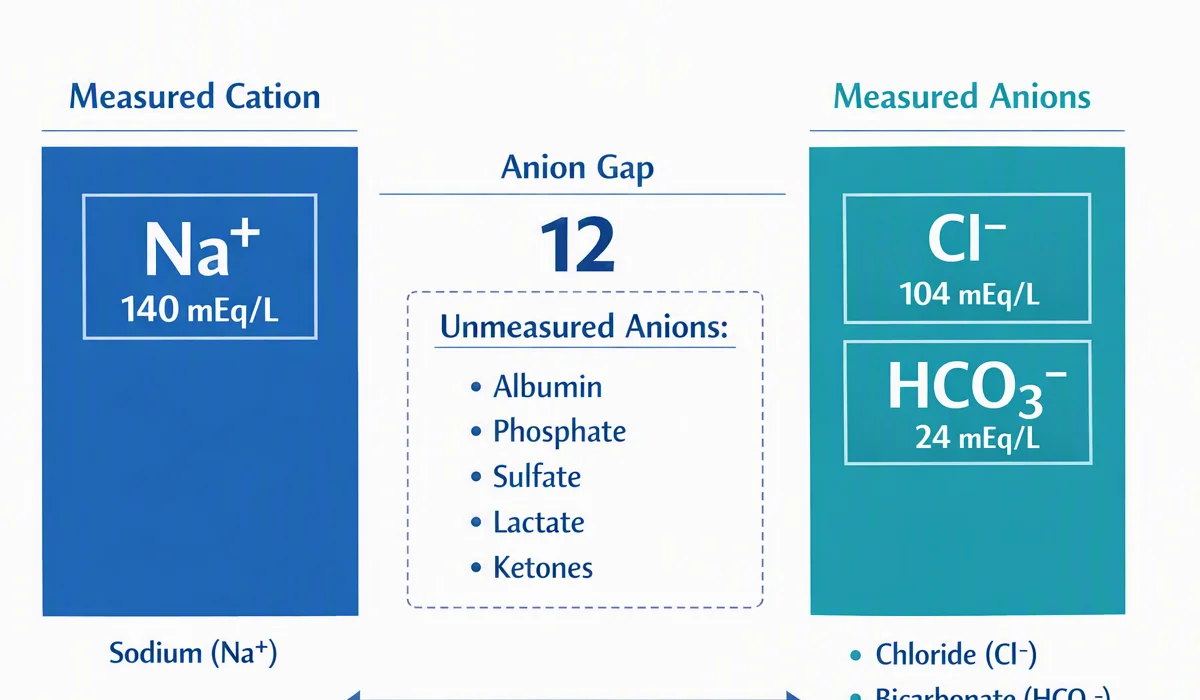
Frequent causes of a high anion gap include:
- Lactic acidosis, which can occur when tissues are not getting enough oxygen or when the body is under significant stress Ketoacidosis, which may happen during diabetes-related illness or prolonged poor intake Kidney disease or kidney failure, when acid removal is impaired Some poisonings or toxin exposures, depending on the scenario
Lactic acidosis can appear when a child is very ill, has poor perfusion, or has another serious condition affecting metabolism. Ketoacidosis is more common when the body is using fat for fuel instead of glucose, which can happen in diabetes or starvation states. Kidney disease can also lead to a rising gap because the kidneys are less able to clear acid effectively.
A high anion gap is not a osmolar gap anion gap comparison diagnosis by itself. It is a clue that supports further evaluation of the child’s symptoms, hydration status, blood sugar, kidney function, and other lab results. This is where diagnostic context matters most.
What Can Cause a Low Anion Gap in Children?
A low anion gap is rarer than a high one, but it can still be important. One of the leading explanations is hypoalbuminemia, or low albumin. Albumin is a important negatively charged protein in the blood, so when it drops, the calculated anion gap can drop as well.
Other possible causes of a low anion gap include:
- Lab error or sample handling issues Low albumin from illness, poor nutrition, or protein loss Paraproteins, which are abnormal proteins that can affect the charge balance More rarely, certain medication or measurement effects
When a low value appears, the first step is often to run the test again or review the original specimen for possible lab error. If the result is real, clinicians may evaluate albumin and consider whether hypoalbuminemia explains the finding.
Because low anion gap results can be caused by technical problems, they are often interpreted carefully. A truly low result may still be clinically meaningful, especially if the child has other abnormalities on the blood test or signs of chronic illness. In some cases, paraproteins are part of the explanation, though this is less common in pediatrics than in adults.
When Should Parents or Doctors Be Concerned?
An abnormal anion gap becomes more alarming when it matches the child’s symptoms or other abnormal lab findings. A number outside the expected reference range doesn’t necessarily mean there is an emergency, but it still means the result should be reviewed with the full picture.
Families and clinicians should pay close attention if the child has dehydration, ongoing vomiting, fast breathing, unusual sleepiness, confusion, poor feeding, or signs of illness that are becoming more severe. These symptoms can point toward a serious metabolic disturbance that needs prompt pediatric evaluation.
Situations that may deserve urgent review include:
- Vomiting with signs of dehydration Difficulty breathing or deep rapid breathing Marked weakness or lethargy Possible diabetic symptoms with concern for ketoacidosis Known kidney disease with worsening lab values
Even without dramatic symptoms, a child with an abnormal result may need follow-up testing if the clinician suspects a developing acid-base problem. The most important question is not simply whether the number is high or low, but whether it corresponds to the child’s overall presentation.
How Doctors Interpret Anion Gap Findings
Doctors assess an anion gap as part of a larger blood test picture. The value assists in assessing acid-base balance, but it is seldom used alone. Instead, the result is matched with the child’s symptoms, exam findings, and other laboratory data.
In many cases, the next step is to examine the full serum chemistry panel and consider whether the child has metabolic acidosis or another acid-base disorder. If the result is above normal, clinicians may investigate lactic acidosis, ketoacidosis, or kidney-related causes. If the result is low, they may check albumin and think about hypoalbuminemia or lab error.
An arterial blood gas may be ordered when the diagnosis is unclear or when the child appears seriously ill. This test is used to evaluate acid-base status more directly and can show whether there is a respiratory component or a mixed disturbance. The anion gap then becomes part of a larger medical interpretation.
It is also important to remember that the anion gap is a calculated value, so it can change if sodium, chloride, or bicarbonate shift. Because of that, clinicians often repeat labs or order follow-up testing when the result does not match the expected picture.
Good interpretation always depends on clinical context. A mild abnormality in a well-appearing child may be less urgent than a similar number in a child with dehydration, vomiting, or other warning signs.
Frequently Asked Questions
What is the normal anion gap for children?
The normal anion gap for children is often comparable to adults, but the exact normal values depend on the laboratory’s reference range. A common range is about 8 to 16 mEq/L when potassium is not included, but local laboratory values should always guide interpretation.
Does the normal anion gap change with age in children?
Yes, it can. The pediatric normal range may vary with age, especially in newborns and infants. Different labs may also use different methods, so age and the testing platform both matter when reviewing pediatric lab tests.
How do you calculate the anion gap?
The usual anion gap formula is sodium minus chloride plus bicarbonate: sodium - (chloride + bicarbonate). An Anion Gap Calculator relies on this formula to produce a calculated value from the blood chemistry results.
What does an elevated anion gap mean in a child?
A high anion gap usually suggests excess acids in the blood and may indicate acidemia. Typical causes include lactate buildup, ketoacidosis, and renal impairment. The result should be interpreted with the child’s symptoms and other lab values.
What does a decreased anion gap suggest in a child?
A decreased anion gap may be caused by low blood albumin, testing error, low blood albumin, or sometimes monoclonal proteins. A repeat test or additional evaluation may be needed to confirm whether the result is real and clinically significant.
Interpreting the anion gap is a useful part of pediatric lab interpretation. When you use an Anion Gap Calculator, the result should always be matched with the child’s symptoms, the full blood chemistry panel, and the broader clinical context. That approach helps clinicians decide whether the finding is a normal variation or a clue to a more important acid-base problem.