Understanding Methanol Poisoning?
Methanol poisoning happens after toxic alcohol consumption of methanol, a substance that can be found in industrial products and contaminated liquids. The danger is not just the methanol itself, but how the body metabolizes it into a harmful byproduct called formate. That process is what drives much of the toxicity, especially the development of acid buildup.
In clinical practice, https://anion-gap-app091.talesignal.com/posts/anion-gap-calculator-using-serum-chloride-for-acid-base-assessment methanol poisoning is a time-sensitive problem because symptoms may appear in stages. Early symptoms can be vague, but as the body processes methanol, the patient may develop worsening acid-base balance problems and signs of end-organ injury. That is why clinical awareness matters so much: the diagnosis can be missed if the exposure history is unclear.
When looking at laboratory results, methanol poisoning is important because it often creates a pattern of high anion gap metabolic acidosis. Such a pattern is a major important clue and often prompts urgent laboratory interpretation, toxicology consultation, and prompt assessment of the patient’s condition.
How Methanol Impacts the Anion Gap
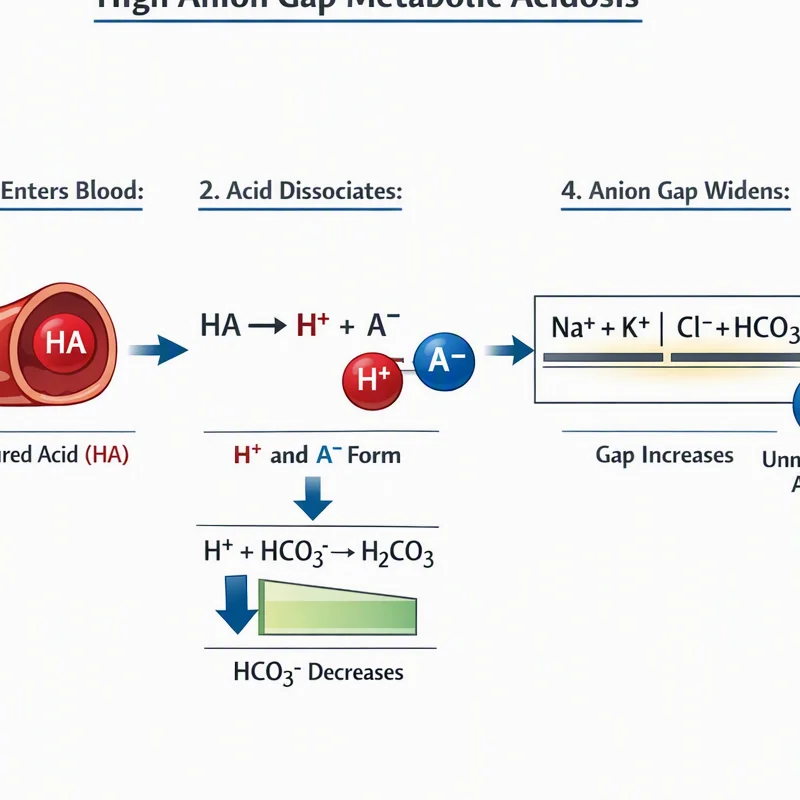
The anion gap reflects the gap between measured ions and measured anions in blood, helping clinicians identify unmeasured anions. In methanol poisoning, the gap rises because methanol is metabolized into formic acid and other acid byproducts that contribute unmeasured acid to the bloodstream. This drives the body toward acidic blood and causes metabolic acidosis.
As formic acid collects, bicarbonate is depleted by the body’s buffering system. That results in a drop in serum bicarbonate, which is a key sign of increasing acid-base disturbance. The anion gap widens because the missing bicarbonate is replaced by unmeasured organic acids, creating a classic acid-base disorder.
This is why methanol poisoning often produces high anion gap metabolic acidosis. The greater the burden of formic acid, the more severe the gap may become. However, timing matters. Early after exposure, methanol can be present before it is fully metabolized, so the anion gap may not yet be greatly elevated. That timing issue is part of why clinicians rely on the whole picture rather than a single number.
In practical terms, the rise in anion gap is a marker of progressive toxicity and helps guide next steps. When the anion gap calculation shows a substantial elevation, clinicians think about methanol among other causes of high-gap acidosis and move quickly to confirm the diagnosis and start treatment.
Why the Anion Gap Calculator Is Significant
An Anion Gap Calculator is valuable because it quickly turns the basic electrolyte panel into a diagnostic tool. By using sodium, chloride, and often potassium along with serum bicarbonate, it helps determine whether a patient may have a concealed metabolic problem. In methanol poisoning, that can be the initial step toward recognizing a severe acid-base disorder.
The calculator is important because it supports bedside laboratory interpretation when symptoms are unclear. A patient with headache, nausea, or confusion may not clearly look poisoned. But if the Anion Gap Calculator shows a high result, that becomes a powerful diagnostic clue that calls for more testing and a careful search for toxic alcohol ingestion.
It also helps clinicians monitor progression. A falling bicarbonate level and rising gap can show that the patient’s condition is getting worse even before severe symptoms appear. In that sense, the calculator is not just for diagnosis; it is part of ongoing rapid assessment and trend interpretation during treatment.
Because methanol poisoning can progress quickly, the gap should be interpreted alongside the rest of the serum electrolytes, symptoms, and exposure history. No calculator replaces judgment, but it can strengthen clinical suspicion and support timely poison management.
Common Test Results in Methanol Toxicity
Common lab results in methanol toxicity may include a elevated osmolar gap early and a elevated anion gap subsequently as formic acid accumulates. The osmolar gap reflects the presence of unmeasured solutes in blood, which may be methanol itself before metabolism is complete. As the toxic metabolite builds up, the picture changes toward metabolic acidosis and a rising anion gap.
An arterial blood gas often shows low pH, confirming acidemia. The blood gas may reveal a reduced bicarbonate level and a marked or large base deficit, which suggests a large acid load. These results align with the broader story of acid-base failure and aid in defining the severity of the crisis.
Another important point is that methanol toxicity can occur alongside or mimic other metabolic problems. For example, lactic acidosis may be present if tissue hypoxia, seizures, shock, or poor perfusion occur. That means the final acid-base pattern may be mixed, and the electrolyte panel should always be interpreted in context.
The combination of an elevated osmolar gap, low pH, low serum bicarbonate, and elevated anion gap strongly supports methanol-related toxicity. Still, the absence of one classic sign does not necessarily exclude poisoning, especially if the patient presents early or has already partially metabolized the alcohol.
How to Interpret a Elevated Anion Gap
A high anion gap means there are extra unmeasured anions in the blood, which usually signals a clinically important acid-base disorder. In methanol poisoning, those unmeasured anions are primarily due to formic acid and related acidic metabolites. The result is a pattern that should quickly raise concern for a toxic ingestion.
To read the finding correctly, clinicians look at the full acid-base picture. Serum chloride may appear somewhat low or unchanged depending on the stage of illness, while bicarbonate is often reduced. The anion gap calculation is therefore a reflection of how the body is compensating, not just a single isolated measurement.
It is also important to understand that not every high anion gap is methanol. The differential diagnosis includes several critical conditions, and the right interpretation comes from combining the laboratory pattern with symptoms, history, and targeted testing. This is where the Anion Gap Calculator becomes a practical tool for guiding next steps.
A high anion gap is a useful clue, not a final diagnosis. In methanol poisoning, it should prompt urgent evaluation for toxic alcohol exposure and other causes of metabolic acidosis.
Methanol Toxicity vs Alternative Causes of Elevated Anion Gap
Various disorders can produce a elevated anion gap, so differentiating methanol poisoning from alternative causes is essential. A key comparison is ethylene glycol poisoning, another toxic alcohol exposure that also results in metabolic acidosis. Both can appear with an elevated anion gap and osmolar gap, but the accompanying findings may differ.
Ketoacidosis is another common cause of high-gap acidosis. Diabetic ketoacidosis or alcoholic ketoacidosis can lead to a substantial elevation in unmeasured acids, but the patient history, glucose level, ketones, and overall presentation usually point in a different direction than methanol exposure.
Uremia can also raise the anion gap, especially in advanced kidney dysfunction, because retained organic acids accumulate when renal clearance falls. In that setting, the lab pattern may resemble poisoning, which is why the full differential diagnosis matters. The calculator can identify the gap, but only careful clinical reasoning can explain it.
Lactic acidosis is another important contender in the differential. It can occur with sepsis, shock, hypoxia, or severe illness and may overlap with methanol toxicity. Because the laboratory pattern can be mixed, clinicians often use toxin screening, repeat blood gases, and trend analysis to clarify the cause. That is part of effective laboratory interpretation and cautious clinical suspicion.
If Methanol Poisoning Becomes an Emergency
Methanol poisoning is a serious emergency when findings or laboratory results suggest major poisoning. Warning signs include eye symptoms, especially vision blurring, because methanol and formic acid can cause damage to the retina. Ocular findings are particularly concerning and may appear alongside headache, confusion, abdominal discomfort, or progressive acidosis.
Symptom progression matters. A patient may first seem only mildly sick, then get worse as formic acid accumulates and the acid-base imbalance worsens. That symptom progression can be swift and life-threatening, which is why toxic alcohol ingestion should never be dismissed when the clinical history is uncertain but the test results fit.
Management usually includes an antidote such as fomepizole treatment, which blocks alcohol dehydrogenase and slows formation of formic acid. In more severe cases, renal replacement therapy is needed to remove methanol and fix the acid-base disturbance more quickly. These interventions are often started based on clear concern rather than waiting for every final test result.
If methanol poisoning is suspected, the poison center and toxicology input are often critical. The combination of elevated anion gap, low bicarbonate, visual symptoms, and possible toxic alcohol exposure should prompt rapid action, because delays can increase the risk of irreversible damage.
FAQ: Methanol Poisoning and Anion Gap
Does methanol poisoning always cause a high anion gap?
No. Methanol poisoning often causes a increased anion gap, but not at first. Soon after toxic alcohol ingestion, the patient may have a unchanged gap before enough methanol has been metabolized into formic acid. As toxicity progresses, the gap usually rises as metabolic acidosis becomes more noticeable.
Why does formic acid increase the anion gap in methanol poisoning?
Formic acid acts as an acid that the body must buffer. As bicarbonate is consumed, serum bicarbonate falls and the blood accumulates unmeasured anions. That shift increases the anion gap and contributes to high anion gap metabolic acidosis.
Can the anion gap be normal early in methanol poisoning?
Yes. The anion gap may be normal early if methanol is still mostly unmetabolized. At that stage, the osmolar gap may be the more helpful clue. As time passes, the osmolar gap may fall while the anion gap rises, so timing is important for laboratory interpretation.
What other lab values should be checked with a high anion gap?
Clinicians usually check an arterial blood gas, pH, bicarbonate, the full electrolyte panel including sodium, chloride, and potassium, plus the osmolar gap. Depending on the case, they may also look for lactic acidosis, ketones, kidney function changes suggesting uremia, and other markers that support the differential diagnosis.
How is methanol poisoning treated when the anion gap is elevated?
Elevated anion gap in methanol poisoning often leads to urgent treatment with fomepizole and, in severe cases, hemodialysis. Supportive care and toxicology-guided management are also important. The goal is to stop further formation of the toxic metabolite, correct the acidosis, and prevent complications such as visual symptoms and retinal toxicity. If methanol poisoning is suspected, immediate evaluation through poison control and emergency care is appropriate.