How do you define the anion gap?
The anion gap is a calculated value that enables clinicians understand the balance of electrolytes in the blood. It is usually derived from the main ions measured on a basic metabolic panel, especially sodium, chloride, and bicarbonate. Because routine lab tests do not measure every charged particle in the blood, the anion gap suggests the amount of unmeasured anions present.
In basic terms, the anion gap helps reveal whether something is missing from the expected acid-base balance. A low or high result does not diagnose a condition by itself, but it acts as an important diagnostic clue in the emergency setting. That is why an anion gap calculator is often used as soon as blood chemistry results are available.
The calculation is often based on the difference between positively charged sodium and the total of chloride plus bicarbonate. Since bicarbonate is a key buffer, changes in its level often indicate a metabolic derangement that needs rapid attention. Emergency clinicians use this value to identify an acid-base disorder before the cause is fully known.
Why ED clinicians turn to an anion gap calculator
Emergency medicine relies on quick recognition of patterns. The anion gap calculator assists clinicians rapidly decide whether a patient may have metabolic acidosis, a potentially dangerous form of acidemia that can occur in critical illness. It is not just a number; it is a tool for clinical decision-making.
If a patient presents with altered mental status, fast breathing, hypotension, or suspected toxin exposure, the anion gap can focus the differential diagnosis. Together with an arterial blood gas and a basic metabolic panel, it helps determine whether the patient has a primary acid-base problem and whether compensation is appropriate. The result can influence triage, the need for repeat labs, and whether advanced critical care support is needed.
The anion gap is especially helpful because it can deliver a faster signal than waiting for a complete workup. If the anion gap is elevated, clinicians may immediately consider lactic acid elevation, ketone production, renal dysfunction, or toxic ingestion. If it is normal, they may shift attention to bicarbonate loss, chloride excess, or a mixed process. That rapid sorting makes the tool valuable in the first minutes of evaluation.
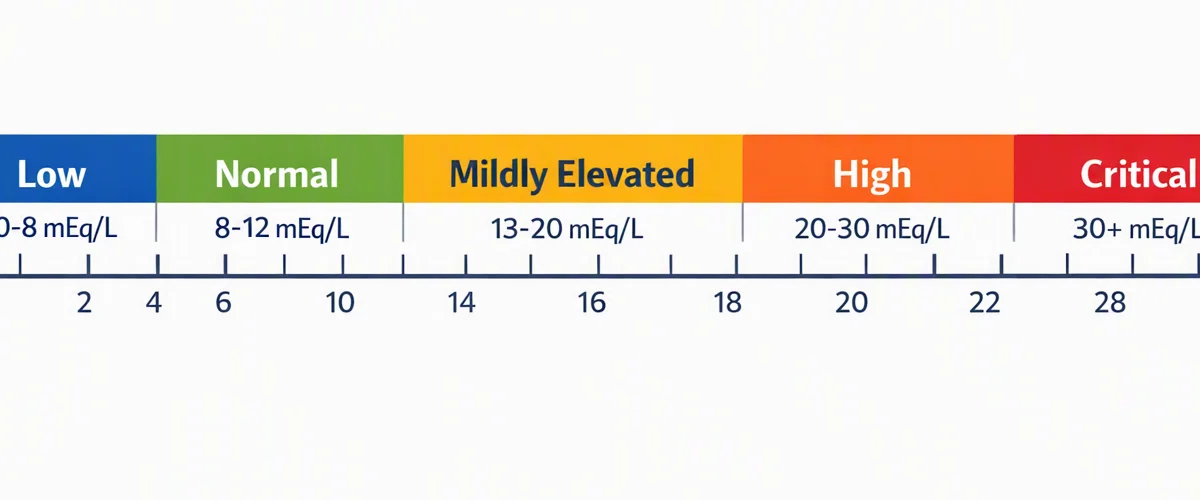
High anion gap vs standard anion gap: what’s the difference?
A high anion gap indicates that extra acids or acid-related compounds are accumulating in the blood. This often happens when there is increased production of acids or reduced clearance of them. Common causes include lactic acidosis, ketoacidosis, and renal failure.
In lactic acidosis, excess lactate builds up when tissues do not receive enough oxygen or are unable to utilize oxygen effectively. In ketoacidosis, the body produces ketones when it cannot use glucose effectively. In renal failure, acid removal is limited, which allows acid compounds to accumulate.
A normal anion gap, often called a non-gap metabolic acidosis, usually points to bicarbonate loss with a compensatory rise in chloride. This is often called hyperchloremic acidosis. In this pattern, the blood may still be acidic, but the missing bicarbonate is replaced by chloride rather than by unmeasured acids. That difference matters because it changes the likely etiology and next tests.
Emergency clinicians use the distinction between high and normal anion gap to guide the workup quickly. A high gap often signals acid accumulation from severe systemic disease or toxin exposure, while a normal gap may suggest gastrointestinal bicarbonate loss or renal tubular problems. In both cases, the anion gap is not the final answer, but it helps identify the direction of the search.
Typical emergency triggers of an elevated anion gap
Various urgent conditions can produce an elevated anion gap, and some require immediate treatment. Amongst the most important are sepsis, shock, toxic alcohols, and salicylate poisoning. Every one can create a serious metabolic state that demands rapid recognition.
Sepsis can trigger lactic acid buildup when infection leads to poor perfusion and impaired oxygen delivery. Shock from any cause can do the same because of tissue hypoperfusion, which raises anaerobic metabolism and lactate production. In these settings, the anion gap may be an early warning sign that the patient is deteriorating even before the full picture is clear.
Toxic alcohols such as methanol or ethylene glycol can produce a marked high anion gap through toxic metabolites. These cases are time-sensitive, and early lab interpretation may be the first clue that a poisoning is present. Salicylate poisoning can also lead to an elevated gap and a complex acid-base pattern, sometimes including respiratory alkalosis and metabolic acidosis together.
Because these causes are potentially life-threatening, an increased anion gap should trigger immediate attention to the patient’s symptoms, vital signs, and exposure history. The Anion Gap Calculator helps clinicians move from a vague complaint to a focused list of dangerous possibilities.
How to interpret the anion gap in clinical context
Understanding the anion gap requires more than looking at a single number. Albumin serves a major role because it is a negatively charged protein that contributes significantly to the gap. If albumin is low, the measured anion gap may seem falsely normal or only mildly elevated even when important acids are present.
For that reason a corrected anion gap is often more revealing than the raw value. Adjusting for albumin enhances lab interpretation and helps reduce missed diagnoses in patients with critical illness, malnutrition, liver disease, or inflammation. A lower albumin level can mask a clinically important acid load.
Another useful concept is the delta gap, which evaluates the change in anion gap to the change in high AG diagnostic meaning bicarbonate. This helps reveal whether another acid-base disorder is also present. For example, a patient may have a high anion gap metabolic acidosis plus a second process such as metabolic alkalosis or normal-gap acidosis.
Clinical context also includes the rest of the lab values. A rising creatinine may support renal failure, a high lactate can support tissue hypoperfusion, and positive ketones can support ketoacidosis. The anion gap is strongest when it is integrated with the patient’s symptoms, history, exam findings, and full electrolyte picture.
When a normal anion gap can still be dangerous
A seemingly normal anion gap does not ensure well-being. Severe illness can still be present even if the number appears reassuring. For example, diarrhea can lead to significant bicarbonate loss and a normal-gap metabolic acidosis that results in acidemia. The patient may be very ill despite a gap that is not elevated.
Renal tubular acidosis is another key cause of normal anion gap acidosis. In this condition, the kidneys cannot appropriately manage acid or bicarbonate handling. Patients may present with weakness, dehydration, or electrolyte abnormalities that call for treatment even though the anion gap does not stand out.
A mixed acid-base disorder can also hide a dangerous process. One disorder may raise the gap while another lowers it, creating a value that looks normal on paper. For example, a patient may have lactic acidosis plus metabolic alkalosis, or a high-gap process plus chloride-driven acidosis. In such cases, the anion gap alone can fail to show the full picture.
Chloride is central to recognizing these cases because increased chloride often accompanies bicarbonate loss. If the clinician only sees a normal anion gap, the underlying problem may be ignored. This is why the electrolyte pattern must always be read as a whole, not in isolation.
Why the anion gap is useful for assessment and treatment decisions
In emergency care, the anion gap helps clinicians decide who needs faster escalation. A markedly elevated gap may indicate a life-threatening process requiring immediate evaluation in critical care. Even before the exact cause is known, the result can justify prompt testing, ongoing monitoring, or ICU-level concern.
The gap also supports early diagnosis. If the clinical picture suggests sepsis, shock, diabetic crisis, poisoning, or renal failure, the anion gap helps reveal that a metabolic process is underway. This can expedite treatment choices such as fluid resuscitation, toxin-specific therapy, insulin, dialysis consultation, or repeat review of acid-base status.
For monitoring, serial anion gaps can help track whether a treatment is working. If the cause is corrected, the gap may decrease as the underlying acid load falls. That trend can be especially helpful in patients with acidemia who are too unstable to wait for slower clinical changes.
Because the anion gap is available from common chemistry testing, it is a reliable tool for bedside decisions. It does not replace the exam or more advanced testing, but it gives emergency teams a fast way to identify the sickest patients and to direct the next diagnostic step.
Constraints of Anion Gap Calculator interpretation
Although useful, the anion gap is imperfect. A laboratory error can create a misleading result, which is why repeat testing is sometimes necessary if the number does not fit the patient's presentation. Issues in specimen handling, contaminants, or transcription problems can all influence interpretation.
The chosen reference range additionally matters. Different laboratories may apply slightly different methods and normal values, so clinicians must interpret the result according to the reporting lab. A value that looks mildly abnormal in one setting may be normal in another.
The difference is also constrained because it captures only some of the chemistry in the blood. Unmeasured ions may accumulate, but the tool cannot identify them directly. It can suggest their existence, yet it cannot identify the exact substance causing the imbalance. That is why the anion gap is a clue, not a definitive answer.
Ultimately, the clinical setting always matters. Someone with nausea and vomiting, diabetes, kidney disease, suspected poisoning, or infection may need additional evaluation whether or not the anion gap is elevated, normal, or borderline. The best interpretation combines the calculated value with symptoms, exam findings, and the broader metabolic picture.
Common questions about anion gap in emergency care
What does the anion gap show in emergency care?
The anion gap lets emergency doctors whether there may be an underlying acid-base disorder that is not obvious from basic chemistry alone. It is a rapid way to look for metabolic acidosis, unmeasured anions, and potential causes such as lactic acidosis, ketoacidosis, renal failure, or toxin exposure. In practice, it assists refine the differential diagnosis and guide urgent next steps.
Why is the anion gap important for diagnosing metabolic acidosis?
The anion gap is useful because it can separate distinct types of metabolic acidosis. A high anion-gap result indicates added acids are building up, while a standard anion gap value suggests bicarbonate loss or chloride gain. This distinction enhances diagnostic value and helps healthcare providers target the correct cause more rapidly.
Can a typical anion gap still suggest an important illness?
Absolutely. A normal anion gap can still be seen in severe conditions such as diarrhea, renal tubular acidosis, or a mixed acid-base disorder. A patient may still have marked acidemia even if the gap is not elevated. That is why acute care teams interpret the anion gap alongside clinical signs, lab values, and the overall clinical picture.
How does albumin affect the anion gap?
This protein influences the expected anion gap because it is a major unmeasured anion in the blood. When albumin is low, the measured anion gap may appear falsely normal. A corrected anion gap accounts for that effect and gives a more accurate estimate of the patient’s acid load.
What causes a high anion gap in the emergency setting?
Frequent causes include lactic acidosis from sepsis or shock, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. These conditions can create a dangerous metabolic derangement that requires prompt recognition. The anion gap calculator helps clinicians notice the pattern early and focus the workup.